
The WAIT Test™ › Wavelengths
Wavelengths in Red Light Therapy: What They Mean, Why They Matter, and How to Evaluate a Device
On this page
- Which red light therapy wavelengths actually work best?
- Where Wavelengths fits in The WAIT Test™
- How to evaluate a device’s wavelengths
- The WAIT Test™ standard for Wavelengths
- Strong disclosure, weak disclosure, and warning signs
- Worked example: which devices pass Wavelengths for a hip?
- The science: why red and near-infrared
- What is a wavelength, and where does red light fit?
- Step 1: Start with light that has a biological impact
- Step 2: Remove light that doesn’t make it to the target tissue
- How common PBM wavelengths compare
- Red light: commonly used for targets closer to the surface
- Near-infrared light: commonly used for deeper targets
- Is a dual-wavelength device better?
- What changes when the patient has fur?
- What does veterinary research show about wavelength?
- Technical details
- Frequently asked questions about red light therapy wavelengths
- Is 660 nm or 850 nm better?
- Is 630 nm different from 660 nm?
- Is 810 nm better than 850 nm?
- Why not use blue or green light for my dog’s joints?
- Does the wavelength work differently on skin, muscle, or bone?
- Does 850 nm reach a joint?
- Can you see 850 nm light?
- Does brighter red light work better?
- Are more wavelengths better?
- Does a laser penetrate farther than an LED at the same wavelength?
- Can I choose a treatment time from wavelength alone?
- The bottom line
- Continue The WAIT Test™
- Research and references
At its core, red light therapy is fairly straightforward: get the right kind of light, in the right amount, straight to the target tissue.
Which red light therapy wavelengths actually work best?
Here is the short answer.
While no single wavelength fixes every tissue or condition, the research gives a clear roadmap.
- Red light, about 620 to 680 nm, is widely studied for wounds, skin, and shallow joints such as the paw, carpus, and tarsus. Common examples: 630, 633, 635, 660, and 670 nm.
- Near-infrared (NIR) light, about 800 to 900 nm, is widely studied and penetrates deeper into tissue. It works for wounds and for deeper targets such as the elbow, stifle, shoulder, hip, spine, muscles, and tendons; it’s the only band that reaches them. Common examples: 808, 810, 830, 850, and 875 nm.
- Not all infrared is the same. The 800 to 900 nm band has the most research. Longer wavelengths like 904, 940, 980, and 1,064 nm, and far-infrared heat, behave differently and need their own evidence. The WAIT Test™ scores superpulsed 905 nm lasers against WALT’s own superpulsed chart; continuous light at 940 nm and longer doesn’t count.
- Blue and green light are biologically active, but they’re absorbed within the first millimeter or two of tissue. They don’t reach deep targets.
- Using both red and near-infrared light is a practical option for a general-use device that needs to reach tissues at different depths.
- But more isn’t always better. If a device uses two wavelengths, the company should explain why each one is there, why they’re emitted at the same time, and how much power each brings to the table.
- Wavelength by itself doesn’t prove a device works. You also need to check power, irradiance, treatment time, area, placement, contact, and schedule. All of these decide how much light actually reaches your target.
For at-home use, if you want to treat both surface and deeper tissues, go with a combo like 660 nm red and 850 nm near-infrared. Both are backed by research. But there’s no proof this exact pair is best for every condition, or that every device with these numbers will work well. If you’re not sure which device or wavelengths to pick for your pet, ask a veterinary clinician.
Where Wavelengths fits in The WAIT Test™
- The right kind of light is the wavelength.
- The right amount is the average power and the irradiance.
- To the target tissue means the light has to actually get there, past fur, distance, and poor placement. Skin contact is the most reliable way to do that.
That one sentence is why MedcoVet built The WAIT Test™.
The WAIT Test™ checks whether a red light therapy device can deliver a useful dose of light to the tissue that needs it. It has four components, and a device must pass all four:
Wavelengths
Is it the right kind of light for the target tissue?
The device must emit red or near-infrared light in a band that counts for the condition.You’re reading this guideAverage Power
Is there enough light to treat the whole area?
The device’s true average optical output must cover the treatment area in one session.Read the guide →Irradiance
Is the light concentrated enough to deliver the dose in time?
The usable light at the skin must deliver the dose at each site within the time limit.Read the guide →Target Tissue
Does the light reach the target tissue?
The light must get past fur and be applied the way the condition needs.Read the guide →Each device is judged separately for each condition and coat, so the same device can pass for a wound and fail for a hip. The full method, including the data you need and the decision rules, is in The WAIT Test™ guide.
This guide covers the first component, Wavelengths. If the light isn’t the right kind, nothing else matters.
This guide starts with how to check a device’s wavelengths, including a worked example. Then it explains the science behind the two bands, and it ends with technical detail for readers who want it.
How to evaluate a device’s wavelengths
Here is a step-by-step checklist to evaluate any light therapy device.
Step 1: Find the exact wavelengths
Look for specific numbers measured in nanometers. Vague marketing terms like “red,” “infrared,” “therapeutic light,” or “medical-grade LEDs” tell you very little about what the device actually delivers.
Step 2: Check for biological impact and a path to the target
For wounds, look for a studied red band (about 620 to 680 nm) or near-infrared band (about 800 to 900 nm). Shallow joints like the paw, carpus, and tarsus can use either. For deeper targets like the elbow, stifle, shoulder, hip, and spine, only near-infrared counts. A broad-use device should cover both regions or clearly support its single-wavelength design. If a device built for joints or muscles leans on blue or green light, ask how that light is supposed to get there.
Step 3: Check the evidence match
Compare the device with the cited research:
- Same wavelength or a clearly justified nearby wavelength?
- Same light source?
- Similar irradiance, dose, and treatment time?
- Same tissue or clinical goal?
- Same species, when veterinary claims are made?
- Same single or combined wavelength setup?
The more a product differs from the study it cites, the weaker the connection between the product and the research.
Step 4: Check dual-wavelength details
Confirm whether both wavelengths run together and how output is divided. A list of wavelengths does not show the dose from each.
Step 5: Complete the WAIT Test™
After wavelengths, assess average power, irradiance, and whether the light reaches the target tissue: gets past fur and is applied the way the condition needs. These factors determine whether an appropriate wavelength becomes a credible treatment delivery system.
The standard
The WAIT Test™ standard for Wavelengths
The Wavelengths component has two checks, plus a third for devices that make pulse-frequency claims. Each is scored separately for every condition.
- W1. Emits a wavelength that counts for this target (20 points). Red (620 to 680 nm) counts only for wounds and shallow joints such as the paw, carpus, and tarsus. Deeper targets (elbow and stifle, shoulder, hip, back and neck, and IVDD) count only near-infrared (800 to 900 nm). The band edges are hard: 875 nm counts, and continuous light at 940 or 980 nm doesn’t. Superpulsed 905 nm lasers are the one exception: WALT gives them their own, lower doses, so their light is scored against WALT’s superpulsed chart. The exact wavelengths have to be known in nanometers.
- W2. No unsupported wavelength claims (5 points). What the company says about its wavelengths has to match what the device emits and what the evidence supports.
W3. No unsupported pulse-frequency claims (5 points). Applies when a company claims special pulse frequencies, such as Nogier “resonance” settings. Claims the evidence doesn’t support cost points.
For a deep target, only the device’s near-infrared output counts in the Average Power and Irradiance dose checks. A red-plus-near-infrared device is judged on its near-infrared share for a hip, but on all of its light for a wound.
Superpulsed 905 nm lasers. A superpulsed laser fires very short, intense pulses at a low average power. WALT’s guidelines give these lasers their own chart with lower doses, for example 3 J/cm² for a hip instead of 9. The WAIT Test™ scores a superpulsed 905 nm laser against that chart and combines its contribution with the device’s other light by its share of the dose. Continuous 905 nm light, and light at 940 nm or longer, doesn’t count.
Wavelength result
Pass or fail, per condition. W1 is worth 20 of the 25 points, so a device whose wavelengths don’t count for the target fails Wavelengths. Missing W2 alone, or W3 alone, costs 5 points and still passes. A device that fails both W2 and W3 fails Wavelengths.
How The WAIT Test™ scores a device. Each device gets one result for each situation (the condition being treated and the coat over the area), not one result overall. Each check is worth a set number of points, and the checks are grouped under the four components. A device passes only if it clears the eye-safety gate and earns at least 75% of the available points in each of W, A, I, and T. It fails if any component stays below 75% even when every missing figure turns out as favorably as possible. If nothing has failed but a missing figure could still decide the result, it needs more information: it can’t pass until the figure is supplied, but it hasn’t failed either. The score out of 100 ranks devices and never overrides the result; when figures are missing, it’s shown as a range. Class 3B and 4 lasers and Risk Group 2–3 LEDs are not safe for home use and aren’t scored. See how every device does, condition by condition, in The WAIT Test™ Device Scorecard.
If the information isn’t available
If a company doesn’t publish its exact wavelengths and they aren’t available from a measurement or a third party, W1 stays open: the device can’t pass until they’re known. Words like “red,” “infrared,” or “deep-penetrating” don’t count.
If a device lists several wavelengths but not how power is split between them, W1 can still pass. The missing split is handled under Average Power (A3): the dose math runs from all near-infrared to none.
The one question to ask
What exact wavelengths does this device produce, and why were they selected for the tissues it claims to treat?
If the exact wavelengths aren’t known from the company, a measurement, or a third party, W1 stays open, and the device can’t pass the Wavelengths part of The WAIT Test™ until they are.
Strong disclosure, weak disclosure, and warning signs
Strong wavelength disclosure
This device uses 660 nm red light and 850 nm near-infrared light. Both wavelengths operate simultaneously. Measured average optical power and surface irradiance include both channels, with each channel’s output contribution reported separately.
Incomplete wavelength disclosure
This device uses therapeutic red and infrared LEDs.
The second statement does not identify the wavelengths, their roles, or their output.
Warning signs
Watch out if a company:
- Lists colors without exact wavelengths
- Says “infrared” without a nanometer value
- Claims a fixed treatment depth from wavelength alone
- Treats visible brightness as proof of optical output
- Claims that more wavelengths always mean a better device
- Promotes blue or green light for deep tissues like joints and muscles
- Cites research that used materially different wavelengths
- Uses evidence for 810 nm as if it directly tested 850 or 980 nm
- Cites a dual-wavelength study to prove one wavelength by itself
- Lists several wavelengths without explaining how power is divided
- Reports peak power while omitting average power
- Gives an emitter count without measured optical output
- Uses cell or rodent research as direct proof of clinical effectiveness in pets
- Claims wavelength alone establishes the dose or outcome
Worked example
Worked example: which devices pass Wavelengths for a hip?
Here’s how W1 plays out for four devices in The WAIT Test™ device comparison, for a 50 lb dog’s hip and for a wound. The hip is a deep target, so only near-infrared (800 to 900 nm) counts. For a wound, red counts too.
| Device | Published wavelengths | W1: hip | W1: wound | Why |
|---|---|---|---|---|
| MedcoVet Luma | 635 nm red + 850 nm near-infrared | Pass | Pass | 850 nm is inside the near-infrared band |
| Multi Radiance My Pet Laser 2.0 | 660 nm red + 875 nm near-infrared | Pass | Pass | 875 nm is inside the 800 to 900 nm band |
| LumaSoothe 2 | 635 nm red + 940 nm | Fail | Pass | 940 nm is outside the band, and red doesn’t count for a hip |
| Dog Med Laser | 635 nm red | Fail | Pass | Red only: it counts for a wound but can’t reach a hip |
Two lessons. First, the band edges matter: 875 nm counts and 940 nm doesn’t. Second, passing Wavelengths says nothing yet about whether there’s enough near-infrared to dose the hip. That’s the job of Average Power and Irradiance.
Deep dive
The science: why red and near-infrared
What is a wavelength, and where does red light fit?
Light travels in energy waves, and a wavelength is simply the distance between the peaks of those waves. We measure them in nanometers (nm), where one nanometer is a microscopic one-billionth of a meter.
Visible light is part of a much bigger family. X-rays, ultraviolet (UV) light, microwaves, and the radio waves that carry TV broadcasts are all the same kind of energy. The only thing that changes is the wavelength (NASA Science).
- Short wavelengths (gamma rays, X-rays, and UV) carry enough energy per photon to damage DNA. That’s why you wear a lead apron for an X-ray and why UV causes sunburn.
- Visible light runs from about 400 nm (violet) to about 700 nm (red). Red is the long end of the visible spectrum.
- Near-infrared starts just past 700 nm, where human vision stops. TV remotes use it, which is why you can’t see the remote’s light (NASA Science).
- Longer still are mid- and far-infrared (felt as heat), then microwaves, then radio and TV waves.
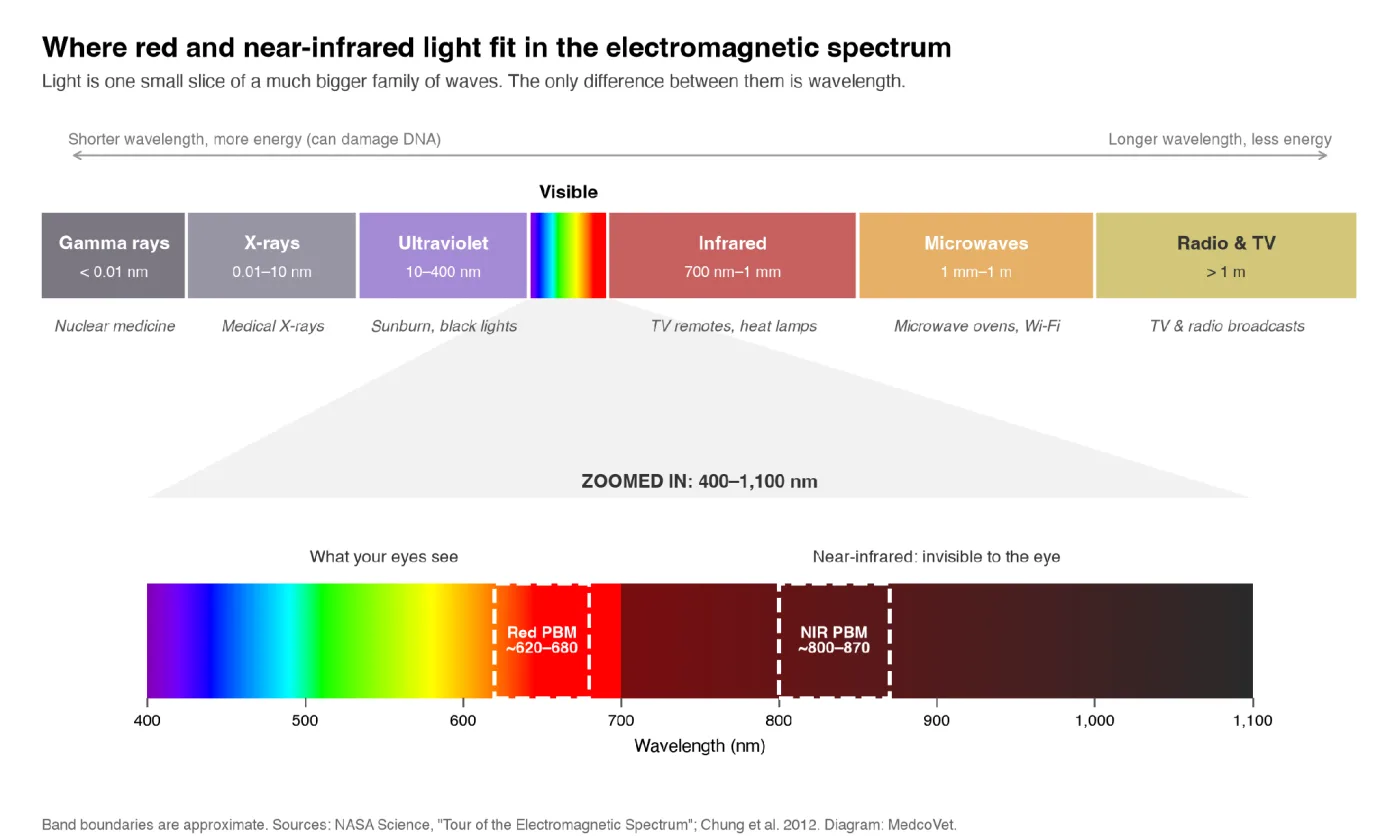
Figure 1. Red and near-infrared light are a narrow slice of the electromagnetic spectrum, between visible light and the heat-carrying far infrared. Band edges are approximate. Diagram: MedcoVet, based on NASA Science and *Chung et al., 2012.*
Red and near-infrared light used in therapy are non-ionizing (Frankowski et al., 2025) (unless in doses over 1M times stronger than typical treatments). Unlike X-rays, they don’t carry enough energy to knock electrons out of atoms or damage DNA (US EPA). At therapeutic doses, their main effect is photochemical, not heating (Chung et al., 2012).
These boundaries are just guidelines, not strict biological limits. A 670 nm photon does not act differently from a 669 nm photon. Also, device output has a range, so the label number usually refers to the peak, not every photon the device emits.
Cool fact: you can see near-infrared light with your phone
Your eyes can’t see 850 nm light, but most phone cameras can. Try it with a TV remote: point it at your phone’s camera, press a button, and watch the screen. The LED flashes on screen, even though it looks dark to your eye.
You can do the same with a red light therapy device. If your device lets you switch the red LEDs off, hold the near-infrared LEDs up to the camera. The “dark” LEDs light up on the screen. If the back camera doesn’t show it, try the selfie camera. Many back cameras have a stronger infrared-blocking filter.
One caution: don’t stare into therapy LEDs, and never point them at your pet’s eyes. And remember that the glow on your screen shows the light is there. It doesn’t measure how much power the device delivers.
Choosing a wavelength comes down to two steps:
- Start with light that has a biological impact. That means light that does something you want, like reducing inflammation, destroying bacteria, or increasing collagen production. Most of that research focuses on red and near-infrared light, but research on blue and green light is growing.
- Remove light that doesn’t make it to the target tissue. Light absorbed by pigment, blood, or water along the way can’t help the target.
Step 1: Start with light that has a biological impact
By “biological impact,” we mean a tangible, helpful change in the tissue—like calming inflammation, clearing out harmful bacteria, boosting collagen, or speeding up cell repair. Not every color of light can pull this off. For light to trigger a real response, a component inside the cell must first absorb its photons. Photobiologists call this fundamental rule the first law of photobiology (Huang et al., 2009). If light passes right through or simply bounces off, it cannot trigger any biological changes. Red and near-infrared light have proven to offer the richest set of cellular benefits, making them the main focus of photobiomodulation (PBM) research ( Hamblin, 2017).
Other colors have a biological impact too, just a different one:
- Blue light (about 400 to 470 nm) kills bacteria and fungi by exciting light-sensitive molecules inside the microbes. Researchers have studied it for acne and infected wounds (Wang et al., 2017c). In cultured human stem cells, blue (415 nm) and green (540 nm) light actually slowed cell growth at doses where red (660 nm) and near-infrared (810 nm) light sped it up (Wang et al., 2017a).
- Green light (about 520 to 540 nm) has reduced pain in rats (Ibrahim et al., 2017) and migraine days in a small human trial (Martin et al., 2021). But it seems to work mostly through the eyes, not by reaching painful tissue.
- Far-infrared light (roughly 3 to 12 µm) is absorbed by water and felt as gentle heat. It’s used in infrared saunas and heat-emitting fabrics, and its effects are tied more to water and warmth than to the mitochondrial pathway below (Vatansever and Hamblin, 2012).
These effects are real, but they aren’t the main tissue-repair story. And as you’ll see in Step 2, blue and green light can’t get very far into the body anyway.
What happens when the light reaches the cell
Here is something that surprises most people: whether you are treating skin, muscle, tendon, bone, or nerve tissue, the light operates through the exact same cellular gateway. It targets the mitochondria—the tiny powerhouses powering nearly every cell in the body.
Inside the mitochondria, an enzyme called cytochrome c oxidase absorbs red and near-infrared light. When it does, two things happen (Chung et al., 2012; de Freitas and Hamblin, 2016):
- Energy goes up. In stressed or injured cells, nitric oxide can clog cytochrome c oxidase. Light can knock it loose, so the cell’s respiratory chain runs faster and makes more ATP, the cell’s energy currency.
- Repair signals go out. The same event releases a short burst of signaling molecules, including reactive oxygen species, nitric oxide, and calcium. These switch on transcription factors such as NF-κB, which turn on genes for cell survival, movement, growth, and new protein production (Hamblin, 2018). In tissue that’s already inflamed, the overall effect is less inflammation: lower levels of inflammatory markers and immune cells shifting toward repair (Hamblin, 2017).
In stressed cells, these effects can also lower oxidative stress, the damaging buildup of reactive oxygen species. Light modulates these molecules (Chung et al., 2012). In healthy cells, it causes a small, useful burst. In stressed cells, it brings their high levels down instead (Huang et al., 2013).
So tissue type doesn’t change what the light does once it arrives. It changes how far the light has to travel.
Researchers have also proposed roles for ion channels, opsins, flavoproteins, and water associated with mitochondrial membranes. Cytochrome c oxidase is therefore best described as the leading mechanism, not the complete or final explanation (Liebert et al., 2022; Sommer, 2019).
What is an action spectrum?
An action spectrum compares how strongly different wavelengths produce a defined biological response under monitored conditions.
In a frequently cited analysis of cultured human cells, response peaks appeared within four bands: about 606 to 624 nm, 668 to 684 nm, 751 to 772 nm, and 813 to 846 nm. These line up with the light-absorbing copper and iron centers of cytochrome c oxidase, and they help explain the repeated use of wavelengths near 630, 660, 810, and 830 nm in PBM research (Karu and Kolyakov, 2005). In practice, the 700 to 770 nm stretch is rarely used (Chung et al., 2012).
The study does not create a universal list of winning wavelengths. It analyzed selected responses in cultured HeLa cells. A wavelength peak can shift with cell type, biological state, measured outcome, dose, and experimental method. An in vitro action spectrum also cannot tell us how much light will reach a tendon, joint, or nerve through intact tissue.
Action-spectrum research provides a scientific reason to choose well-studied bands rather than random colors. Still, clinical and veterinary research needs to test full treatment protocols in real patients.
Step 2: Remove light that doesn’t make it to the target tissue
Once you have light with a biological impact, remove the light that can’t reach the target. Light absorbed along the way never arrives.
When light enters the body, each photon does one of a few things:
- It passes through. Some light makes it all the way through without being absorbed. That’s why your fingertip glows red when you hold it over a red light. Try the same thing with green light, and you’ll see almost nothing, because blood absorbs nearly all of the green before it gets through.
- It bounces off. Light can hit a cell or another tissue structure and change direction. This is called scattering. In tissue, it happens over and over, which is why light spreads out and fades as it goes deeper.
- It gets absorbed. A molecule takes in the photon’s energy. Some molecules then give off a new photon with less energy (fluorescence), but in PBM that effect is small.
So in PBM, it mostly comes down to passing through, bouncing, or absorbing. Only absorption can change how a cell works, and only when the right molecule absorbs it. When cytochrome c oxidase in the mitochondria absorbs light, it triggers the two effects described in Step 1: more ATP and repair signals. When melanin, hemoglobin, or water absorbs it along the way, the energy mostly becomes a tiny amount of heat and never reaches the target tissue.
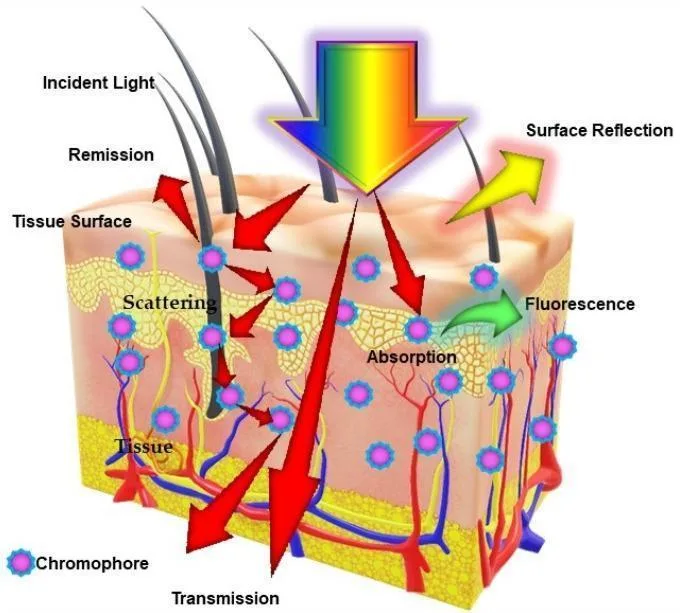
Figure. What happens when light meets tissue: reflection, scattering, absorption, fluorescence, and transmission. Image: Sarbadhikary et al., Theranostics 2022, CC BY 4.0. **Source
Wavelength changes the balance among these events. In the body, two groups of absorbers do most of the stealing:
- Below about 600 nm: melanin and hemoglobin. Melanin is the pigment in skin and in your pet’s coat. Hemoglobin is the red pigment in blood. Both absorb blue and green light very strongly, so those colors get used up in roughly the first millimeter or two.
- Above about 1,000 nm: water. Soft tissue is mostly water. Water absorbs very little red light, but its absorption has a small bump near 970 nm and climbs steeply past about 1,100 nm.
Between them is a broad optical window, roughly 600 to 1,070 nm, where light travels farthest through tissue (Chung et al., 2012). Classic and modern tissue-optics research places it within the red and near-infrared spectrum, though the exact edges vary by tissue and measurement method (Anderson and Parrish, 1981; Jacques, 2013).
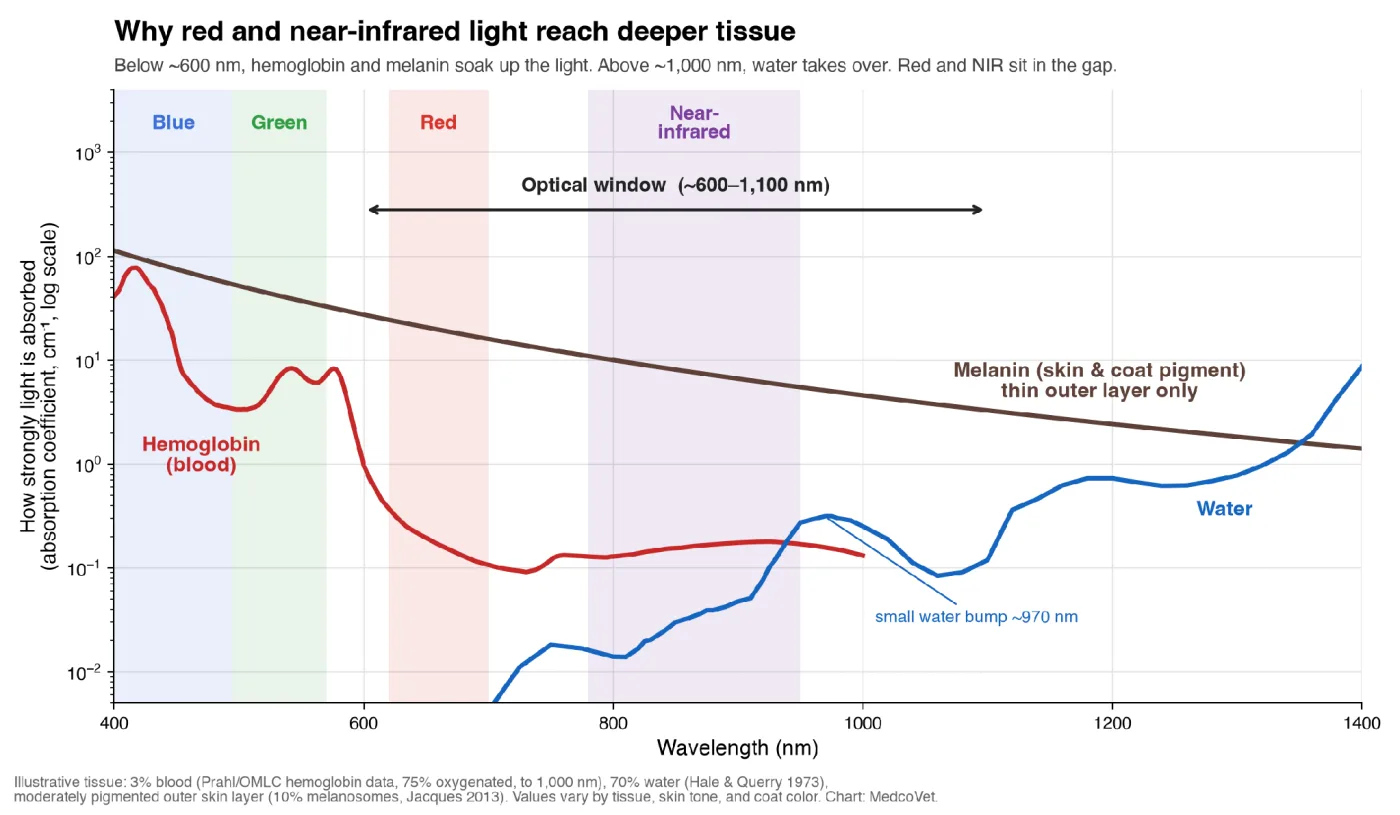
Figure 2. How strongly the body’s main light absorbers soak up each wavelength. Blue and green light are absorbed heavily by hemoglobin and melanin. Water takes over at long wavelengths. Red and near-infrared light fall in the low-absorption gap. Illustrative tissue (a modeling assumption): 3% blood, 70% water, and a moderately pigmented outer skin layer. Data: *Prahl (OMLC), Hale and Querry, 1973, and Jacques, 2013. Chart: MedcoVet.*
Melanin doesn’t switch off at 600 nm. It fades gradually. Its absorption is roughly two to three times higher at 660 nm than at 850 nm, so the outer skin layers absorb more red light before it reaches deeper tissue (Jacques, 2013). That’s also why dark skin and dark coats still absorb some near-infrared light, and why parting the fur matters so much for pets.
The numbers are large. Across 400 to 1,000 nm, darker human skin absorbs about 6% to 74% more light than lighter skin, and light passes through best beyond about 940 nm for every skin type (Setchfield et al., 2024). In cell studies, placing melanin filters in front of 670 nm light reduced the cells’ response in proportion to the amount of melanin (Brondon et al., 2007).
The result is simple to see. In a computer model of human skin, blue light barely reached 1 mm, while red light reached about 4 to 5 mm before fading out (Ash et al., 2017).
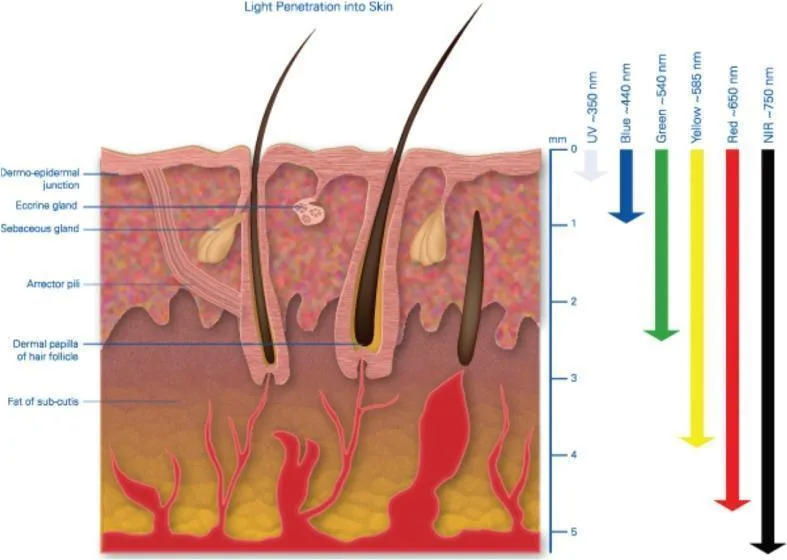
Figure 3. Approximate depth each color reaches in human skin. Ultraviolet barely enters. Blue reaches about 1 mm. Red reaches about 4 to 5 mm, and near-infrared goes farther. Source: *Ash C, Dubec M, Donne K, Bashford T. Lasers in Medical Science, 2017. © The Authors, licensed under CC BY 4.0.*
Near-infrared light can travel much further in some tissues. In human cadaver heads, 808 nm light was detected about 40 mm deep, through the scalp, skull, and brain (Tedford et al., 2015). A 2025 study found that longer wavelengths in sunlight pass through the human body (Jeffery et al., 2025).
Here’s the simple takeaway. Tissue transmission and biological absorption are related, but they’re not the same. Just because a wavelength travels farther doesn’t mean it’s the best choice for your target tissue. You need both: light that affects biology and light that reaches the target tissue.
What’s left for each target
- Wounds and skin: Red and near-infrared both work. The target is at the surface, so red light doesn’t have far to travel, and red is well studied for wound and skin repair (Yadav and Gupta, 2017). Near-infrared works too: in one mouse wound study, 810 nm gave the strongest healing response (Gupta et al., 2014).
- Shallow joints (paw, carpus, tarsus): Red and near-infrared both reach these joints, which sit close to the skin.
- Deeper joints, the spine, muscles, tendons, and nerves: Only near-infrared makes it that deep. Blue and green are absorbed near the surface, and red fades within a few millimeters.
- Not all infrared is the same: The 800 to 900 nm band is the best studied. Wavelengths near 980 nm sit on water’s absorption bump and work partly by heating. Water absorbs far-infrared near the surface, so it feels like warmth rather than penetrating deep.
How common PBM wavelengths compare
Once you group wavelengths by what actually changes, the picture gets simpler. Within red (about 620 to 680 nm), the differences are small. The same is true within near-infrared (about 800 to 900 nm). The big jumps happen between colors.
| Band | Common examples | How far it gets | Commonly used for | The catch |
|---|---|---|---|---|
| Blue ~400–495 nm | 405, 415, 450 nm | Least. About 1 mm in skin (Ash et al., 2017) | Killing surface bacteria; acne; infected wounds (Wang et al., 2017c) | Heavily absorbed by melanin and blood. Slowed stem-cell growth where red stimulated it (Wang et al., 2017a) |
| Green ~495–570 nm | 525, 532, 540 nm | Shallow. Strongly absorbed by hemoglobin | Pain and migraine research, mostly through the eyes (Ibrahim et al., 2017; Martin et al., 2021) | Not a way to reach muscles or joints |
| Red ~620–680 nm | 630, 633, 635, 660, 670 nm | Several millimeters; best for surface and near-surface targets | Wounds, skin, and shallow joints (paw, carpus, tarsus). Also incisions and surface inflammation; 670 nm in neurologic and retinal research | 660 nm passes a bit better than 630 nm because blood absorbs less, but no consistent evidence shows one red beats another |
| Near-infrared~800–900 nm | 808, 810, 830, 850, 875 nm | Deepest of the four. Still, more than 90% of laser energy was absorbed within the first 10 mm in one ex vivo study (Kaub and Schmitz, 2022) | Wounds too, and the only band that reaches deeper joints, the spine, muscles, tendons, ligaments, and nerves | 810 vs. 850 nm differences are small. Nearby-wavelength evidence is supportive, not identical |
Why only one red row and one near-infrared row? Because the numbers inside each band are close. Melanin absorbs only about 1.2 times more at 630 nm than at 660 nm, and about 1.2 times more at 810 nm than at 850 nm. Compare that with about 2.4 times more at 660 nm than at 850 nm (Jacques, 2013). Hemoglobin shows a bigger gap within red: whole blood absorbs about 1.6 to 1.9 times more at 630 nm than at 660 nm (Prahl, OMLC), which is one reason 660 nm is so popular. The action spectrum also shows separate peaks near 620 and 670 nm (Karu and Kolyakov, 2005). But no consistent head-to-head clinical evidence picks a winner inside either band.
Some longer near-infrared wavelengths are special cases. They behave differently enough that they deserve their own rows. The WAIT Test™ counts only 800 to 900 nm as near-infrared, so 875 nm counts. Superpulsed 905 nm lasers are scored separately, against WALT’s superpulsed chart, and continuous light at 940 nm and longer doesn’t count:
| Wavelength | Typical use | Evidence | Main caution |
|---|---|---|---|
| 904 to 905 nm | Often used in superpulsed laser systems | Clinical and preclinical research exists for specific pulsed protocols | Peak power, pulse width, frequency, and average power are central to interpreting the wavelength |
| 940 to 980 nm | Longer NIR designs | Can produce biological effects through mechanisms that may differ from 810 nm | Water absorption and heating become more important; evidence from 810 or 850 nm cannot simply be transferred |
| 1,064 nm | Used in some deeper-tissue and neurologic systems | Some transmission and clinical research is available | It sits outside the best-known PBM action bands and needs use-specific support |
These tables provide scientific context. They are not a treatment chart.
Red light: commonly used for targets closer to the surface
Visible red PBM commonly uses wavelengths from about 620 to 680 nm. Frequently studied examples include 633, 635, and 660 nm. The original PBM workhorse, the helium-neon laser, emitted at 632.8 nm (Chung et al., 2012).
Red light is often selected for:
- Wounds and incisions
- Skin and other superficial tissues
- Surface inflammation or irritation
- Structures located close to the skin
- Shallow joints such as the paw, carpus, and tarsus
- Treatment areas where visible placement feedback is useful
Red wavelengths still go into tissue. Calling them “superficial” just means they target areas near the surface, not that red light only works at the surface.
With irradiance and surface energy density held constant, 635 and 810 nm improved healing measures, while 730 and 980 nm did not under the same tested settings. The strongest response occurred at 810 nm (Gupta et al., 2014).
Non-invasive red and near-infrared exposure has also been reported to support wound healing in animal models of impaired cutaneous repair (Yadav and Gupta, 2017).
In cultured human adipose-derived stem cells, both 660 and 810 nm increased ATP and proliferation under the study conditions (Wang et al., 2017a).
These studies support the biological activity of red and near-infrared bands. They also show why a result belongs to the wavelength, dose, model, and outcome that were actually tested.
Near-infrared light: commonly used for deeper targets
Near-infrared light is outside normal human vision. PBM devices use several near-infrared bands, with 808, 810, 830, and 850 nm among the most common in research and consumer devices.
For inflammation below the skin, near-infrared reaches the target tissue. It is often selected for:
- Muscles
- Joints
- Tendons and ligaments
- Nerves
- Deeper areas of pain or inflammation
- Anatomical sites with several layers above the target
Wavelengths around 800 to 900 nm usually pass through tissue better than visible red light. But that doesn’t mean there’s a set treatment depth, or that all light reaching deeper tissue is still useful. And not all infrared is the same: the longer wavelengths covered below work differently.
Does research support 850 nm?
Yes, with an important qualification.
Wavelengths around 810 to 850 nm sit within a well-studied near-infrared region. Laboratory, animal, and human studies report biological effects across this range. A randomized, double-blind, placebo-controlled crossover trial used an LED cluster combining 660 and 850 nm before a knee-extensor fatigue test and found less torque loss after exercise (Baroni et al., 2010).
That trial supports a 660 and 850 nm combination protocol. It cannot isolate the effect of 850 nm because both wavelengths were delivered together. Evidence from nearby wavelengths, especially 810 and 830 nm, strengthens the scientific basis for the region but should not be presented as direct proof for every 850 nm device.
This difference matters when you look at product claims. Evidence for a wavelength range can back up a design choice. But evidence for a specific emitter, output, dose, and clinical use is even stronger.
Is a dual-wavelength device better?
Sometimes, a dual-wavelength device is the smarter design. But you have to prove it’s better, not just assume.
A device that combines red and near-infrared light can provide:
- Coverage over a broader range of tissue depths
- A way to address treatment areas containing skin, connective tissue, muscle, and joint structures
- Simpler home use when the user should not have to select a wavelength for each placement
- Access to two well-studied portions of the PBM spectrum
Research on multiwavelength PBM reports that combinations can produce different effects from single wavelengths, including additive, complementary, or occasionally opposing responses. Results depend on the wavelengths, sequence, timing, dose from each source, and biological model (Lima, Sergio, and Fonseca, 2020).
The takeaway: using two wavelengths can be a smart way to cover different tissue depths. But more wavelengths don’t automatically mean better quality. For example, adding blue or green to a deep-tissue device wastes power on light that won’t reach the target.
What a dual-wavelength company should disclose
Ask:
- Do both wavelengths operate at the same time?
- Can they be selected separately?
- How many emitters produce each wavelength?
- How much average optical power comes from each wavelength?
- Is the stated irradiance measured with both wavelengths active?
- Does the cited research use both wavelengths together?
- Is the dose calculated from the combined output or from one channel?
A device may advertise five wavelengths while delivering most of its power through only one. An emitter count also does not answer the power question because different LEDs can have different outputs.
What changes when the patient has fur?
Fur blocks light in two ways. Its pigment absorbs light (that’s the melanin from Step 2), and the coat’s density and structure physically block and scatter it. Choosing a longer, near-infrared wavelength can reduce the pigment-related loss somewhat, since fur melanin absorbs less at longer wavelengths just as skin melanin does. But it does not fix the physical blocking caused by a thick or unshaved coat.
In a study of 47 dogs, wavelength, coat color, shaving, and device power significantly affected measured light transmission. Under the tested conditions, darker and unshaved coats transmitted less light. Coat length itself was not a significant predictor in that study (Hochman-Elam, Heidel, and Shmalberg, 2020).
This doesn’t mean coat length never matters. In this study, pigment and whether the dog had hair explained more of the difference.
In practice, getting light past fur comes down to application: parting the coat, contact, and placement. The Target Tissue guide covers that in detail.
Skin pigment also affects absorption and heating. A human study comparing red and infrared laser transmission found that skin color and tissue thickness influenced transmittance, reflectance, and temperature response (Souza-Barros et al., 2018). The same surface setting should not be assumed to deliver the same target-tissue dose in every patient.
What does veterinary research show about wavelength?
Veterinary PBM research supports continued clinical interest, but it does not identify one best wavelength for every species, condition, or tissue.
A 2023 systematic review included 45 veterinary articles published from 1980 through 2020: 24 involved dogs, one involved cats, and the remainder involved horses. The authors found conflicting results, wide variation in wavelength, laser class, dose, session frequency, and treatment duration, and generally moderate or high risk of bias (Millis and Bergh, 2023; Bunch, 2023).
That evidence gap matters in three ways:
- A human study can support a mechanism or wavelength rationale, but it is not direct clinical proof for dogs or cats.
- A canine study using one full protocol cannot show that wavelength was the only reason for the result.
- Feline evidence is especially limited, so dog protocols should not be treated as proven cat protocols.
The good news: the cell-level mechanism from Step 1 is the same in people, dogs, and cats. Mitochondria and cytochrome c oxidase work the same way across mammals. What differs is the path to the target: coat, skin thickness, body size, and anatomy.
Newer veterinary research continues to add condition-specific data. A 2026 prospective multicenter pilot study tested a dual 808 and 905 nm PBM protocol in 22 dogs with otitis externa. Clinical scores and yeast counts improved across five sessions, with no adverse events reported. The study had no sham control; some ears also received a cleanser, and the authors called for controlled trials, so read this as early evidence for that exact protocol rather than proof for all dual-wavelength devices (Gesuete et al., 2026).
The honest answer is that choosing wavelengths for veterinary care should be based on the best available evidence from tissue optics, lab studies, human research, and veterinary studies. It is important to clearly state what kind of evidence supports each claim.
Technical reference
Technical details
How far does red or near-infrared light penetrate?
There is no simple, universal answer for how many millimeters red or near-infrared light can penetrate. Statements like “light penetrates 10 mm” or “850 nm reaches 40 mm” treat a changing photon distribution as if light stops at a fixed line. It does not. Light generally weakens as it travels. A small fraction may be measured beyond the depth where most of the original energy has already been absorbed or scattered away.
Penetration depends on:
- Wavelength
- Tissue type and thickness
- Blood content and oxygenation
- Water and fat content
- Melanin and skin pigment
- Fur or hair between the emitter and skin
- Contact versus non-contact use
- Beam size and geometry
- Angle and pressure
- Power and irradiance at the surface
- The definition of “penetration” used by the researcher
That last point matters more than it sounds. When researchers attach a precise meaning to “penetration depth,” the standard diffusion-theory definition is the depth at which irradiance falls to 1/e (about 37%) of its surface value (Jacques, 2013). Other studies instead report the depth at which only 10% or 1% remains, which yields a much larger number for the same light and tissue. The skin-model figures above, for example, use the 1% definition (Ash et al., 2017). A bare figure in millimeters that doesn’t say which of these it means can’t be compared to a different bare figure in millimeters.
A review of head-tissue studies found very large differences in measured red and near-infrared transmission across species, anatomical sites, and experimental methods (Salehpour et al., 2019). In an ex vivo study of several animal tissues and two commercial near-infrared laser systems, more than 90% of measured light energy was absorbed within the first 10 mm, with very little left after 15 to 20 mm under the tested conditions (Kaub and Schmitz, 2022). That result should not be converted into a rule for every device or patient. It shows why surface output and target-tissue dose are different quantities.
Beam size matters too, but only up to a point. In the same skin model, a 10 mm-wide beam delivered 73% to 88% of the light an infinitely wide beam delivered at 1 to 3 mm deep. Going wider than that added little (Ash et al., 2017).
Penetration and effectiveness are not the same thing
A comparative animal study illustrates the point. At the spinal cord injury site, more 830 nm photons arrived than 670 nm photons. Yet 670 nm performed better for some optic-nerve and retinal outcomes, and neither wavelength improved the tested traumatic brain injury or spinal cord injury outcomes under those protocols (Giacci et al., 2014).
Deeper transmission can be useful when the target is deep. Biological response, delivered dose, and protocol are still essential.
What is different about 904, 905, 980, and 1,064 nm?
904 and 905 nm
These wavelengths commonly appear in superpulsed laser systems. A very short pulse can have high peak power while the average power across the full treatment remains much lower. When reading research on these systems, consider pulse width, repetition rate, duty cycle, average power, beam area, and dose. Quoting the wavelength or peak power alone leaves out most of the protocol.
Water absorption is somewhat higher at 904 to 905 nm than at 850 nm, which alone would suggest slightly shallower penetration. But water is only one factor. Melanin and hemoglobin absorb less at 904 to 905 nm than at 850 nm, and scattering is somewhat lower too, so these effects roughly offset the water difference. The net penetration difference between these two wavelengths is modest and depends on the tissue, so neither is a clear win. The bigger practical issue is duty cycle. A superpulsed laser can deliver many watts of peak power at a duty cycle well under 1%, leaving the average power delivered to tissue far lower, often by several orders of magnitude, than a continuous-wave source at a similar wavelength. Whatever small penetration difference exists between these wavelengths is easily outweighed by that gap in total photons delivered.
For scoring, The WAIT Test™ follows WALT: a superpulsed 905 nm laser is judged against WALT’s superpulsed chart, which uses lower doses (3 J/cm² for a hip instead of 9), and its contribution is combined with the device’s other light by its share of the dose. A continuous 905 nm source doesn’t count.
980 nm
At 980 nm, you’re sitting right on water’s small absorption bump (see Figure 2), so water absorbs more light than it does around 810 nm. In cell research comparing 810 and 980 nm, the authors reported evidence of different dominant mechanisms: 810 nm effects were linked mainly to cytochrome c oxidase. In contrast, 980 nm effects were linked more strongly to temperature-sensitive calcium channels (Wang et al., 2017b).
This does not mean 980 nm is ineffective. It means you should not assume results from 810 or 850 nm apply to 980 nm without careful review. Pay close attention to heat and all device settings.
1,064 nm
Research has tested 1,064 nm for deeper transmission and for selected clinical uses. One ex vivo comparison found better transmission through the upper 10 mm of tested tissues at 1,064 nm than at 905 nm, while the advantage did not continue uniformly at greater depths (Kaub and Schmitz, 2023).
As with every less-common wavelength, the right question is not whether 1,064 nm can enter tissue. Ask whether the company can support its use for the claimed target with the same wavelength and a comparable delivery protocol.
Peak wavelength, tolerance, and spectral width
This is an advanced topic, and most people don’t need to worry about it. Most light sources sold today are well within what red light therapy needs.
For completeness, here’s what’s going on. When a light is sold as a certain wavelength, such as 660 nm, that number is the peak, where output is strongest. A good LED usually hits its rated peak within a few nanometers and spreads a little light to either side.
Light sources didn’t always look like this. Before LEDs took over, many light therapy devices used filtered lamps that spread their output across hundreds of nanometers. LED-based PBM only started appearing regularly in research after about 2001 (Heiskanen and Hamblin, 2018). Today’s LEDs put nearly all of their output inside the band they’re sold for.
Lasers have always been very narrow. A diode laser’s output is typically just 1 to 2 nm wide (Heiskanen and Hamblin, 2018). Modern LEDs are still a bit wider, but their output stays within the same red or near-infrared band. That’s why today’s LEDs are much more comparable to lasers than older light sources.
Laser versus LED: does the wavelength mean the same thing?
A nanometer is the same unit whether the source is a laser or an LED. The sources differ in other ways.
Lasers typically produce a narrow spectral band and can be highly directional and coherent. LEDs generally produce a more extensive spectral band and a more divergent beam. Device design affects beam shape, treatment area, irradiance, heating, and how light reaches the surface.
Neither lasers nor LEDs work just because of their name. A review comparing the two concluded that PBM doesn’t depend on lasers or coherence, though few head-to-head comparisons were well matched (Heiskanen and Hamblin, 2018). LEDs have shown results in controlled studies, like the 660 and 850 nm muscle trial mentioned earlier. You cannot assume results from laser studies apply to LED devices with different beam areas, outputs, distances, or doses, and the reverse is also true.
When comparing studies or products, match the full treatment as closely as possible (Jenkins and Carroll, 2011):
- Wavelength
- Light source
- Average power
- Irradiance at the treatment surface
- Beam or treatment area
- Continuous or pulsed delivery
- Treatment time
- Energy and energy density
- Contact, distance, and pressure
- Anatomical site
- Number and timing of sessions
Why wavelength is necessary but not sufficient
Choosing the right wavelength tells you the type of light you are using, but it does not tell you whether enough useful light is actually hitting the target area.
Plenty of devices proudly list standard 660 nm and 850 nm wavelengths, yet they can end up delivering vastly different results in practice.
How much light a device puts out, and how concentrated it is at the skin, are covered in the Average Power and Irradiance guides. Wavelength only sets what kind of light it is.
FAQ
Frequently asked questions about red light therapy wavelengths
Is 660 nm or 850 nm better?
Neither is universally better. They serve different optical roles. A 660 nm red wavelength is commonly used for surface and near-surface targets. An 850 nm near-infrared wavelength generally penetrates farther and is commonly used for deeper tissues. A device may combine them when the treatment area contains tissues at several depths.
Is 630 nm different from 660 nm?
Only a little. Both are in the red band, both line up with cytochrome c oxidase absorption, and both are widely studied. Blood absorbs less at 660 nm, so it penetrates tissue slightly better (Prahl, OMLC). No consistent clinical evidence shows that one beats the other. The power and dose a device delivers matter more than a 30 nm difference.
Is 810 nm better than 850 nm?
810 nm has a large body of mechanistic and clinical research. 850 nm sits close to the well-studied 813 to 846 nm action band and appears in controlled combined-wavelength LED trials. Direct head-to-head evidence is too limited to declare one universally superior. Device output, dose, target tissue, and protocol can matter more than a 40 nm difference. Also, an LED labeled 850 nm emits across a band roughly 20 to 30 nm wide, so part of its light falls inside that 813 to 846 nm band.
Why not use blue or green light for my dog’s joints?
Because it won’t get there. Melanin in the coat and skin, and hemoglobin in the blood, absorb blue within roughly the first millimeter or two and green light slightly farther (Ash et al., 2017). Blue light has real uses at the surface, like killing bacteria, but it isn’t a deep-tissue tool.
Does the wavelength work differently on skin, muscle, or bone?
Not at the cell level. In all tissues, red and near-infrared light mainly act on mitochondria. They raise ATP and trigger signals that support repair and calm inflammation (Hamblin, 2017). What changes from tissue to tissue is how much light reaches it.
Does 850 nm reach a joint?
Some 850 nm photons can reach deeper tissue, but you can’t know how much reaches a particular joint from wavelength alone. Joint depth, anatomy, fur, pigment, body composition, contact, irradiance, beam area, and treatment time all affect delivery.
Can you see 850 nm light?
Not really. Near-infrared light is outside normal human vision. Some 850 nm emitters show a faint red glow from the edge of their emission spectrum. Your phone camera can see it, though. If your device allows it, turn off the red LEDs and hold the near-infrared side up to the camera. The LEDs will light up on screen. It works with a TV remote too. Visible brightness, on-screen or in person, does not measure near-infrared power.
Does brighter red light work better?
Brightness is a visual perception, not a therapeutic measurement. Your eyes cannot see the near-infrared portion of a device’s output. Compare measured wavelength, average optical power, irradiance, area, and dose.
Are more wavelengths better?
No general rule supports that claim. Each added wavelength should have a defined role, meaningful output, and evidence that fits the intended use. Extra wavelengths can divide a device’s total power without improving the treatment.
Does a laser penetrate farther than an LED at the same wavelength?
Light-source design affects direction, beam shape, divergence, spectral width, and surface irradiance. These factors can change delivery. The word “laser” alone does not state penetration or clinical effectiveness. Compare measured beam and dose parameters under the same treatment conditions.
Can I choose a treatment time from wavelength alone?
No. Time depends on irradiance, treatment area, intended dose, tissue, patient, condition, and protocol. Two 660 nm devices can require very different treatment times because their measured output differs.
The bottom line
When evaluating any red light therapy device, the first thing I check is its wavelength specifications.
Start with light that has a biological impact: red and near-infrared light are absorbed by mitochondria in nearly every cell, where they increase energy production and send repair and anti-inflammatory signals. Then remove light that doesn’t reach the target: melanin and blood soak up blue and green, and water soaks up long infrared. What’s left is two bands. Red around 620 to 680 nm works for wounds and shallow joints such as the paw, carpus, and tarsus. Near-infrared around 800 to 900 nm also works for wounds, and it’s the only band that reaches deeper targets like the elbow, stifle, shoulder, hip, and spine. Not all infrared is the same. A combined red and near-infrared device can be a sensible choice when one treatment area contains structures at different depths.
The label ought to match the real treatment. Ask for the exact wavelengths, proof that the same light was used in studies, how much output comes from each wavelength, measured irradiance, treatment time, placement, and how the light actually gets to the skin. For pets, think about fur management and a plan that fits their anatomy and clinical needs.
The goal is simple. Get the right kind of light, in the right amount, to the tissue you want to help. Wavelength tells you if that’s even possible. The rest of The WAIT Test™ shows if the device can actually deliver.
Continue The WAIT Test™
This guide covers Wavelengths, the first of the four components. To run the full evaluation, including the data you need and the decision rules, use The WAIT Test™ guide. The other three components:
- Average Power: Is there enough light to treat the whole area?
- Irradiance: Is the light concentrated enough to deliver the dose in time?
- Target Tissue: Does the light reach the target tissue?
The WAIT Test™ was developed by MedcoVet. It is an educational framework for comparing device specifications. It does not determine whether PBM is appropriate for a specific pet, person, diagnosis, or treatment area. Make treatment decisions with a qualified veterinary or healthcare professional.
For every WAIT guide and tool in one place, start at The WAIT Test™ hub.
Ready to take the next step?
Book a free consultation with a licensed MedcoVet clinician to discuss your pet’s condition and receive a custom at-home plan.
Apollo
Learn more about the MedcoVet Luma, which uses 635 nm red light and 850 nm near-infrared light together.
Sources
Research and references
- Anderson RR, Parrish JA. The optics of human skin. Journal of Investigative Dermatology. 1981;77(1):13-19. PubMed
- Ash C, Dubec M, Donne K, Bashford T. Effect of wavelength and beam width on penetration in light-tissue interaction using computational methods. Lasers in Medical Science. 2017;32(8):1909-1918. PubMed Central
- Baroni BM, Leal Junior ECP, Geremia JM, Diefenthaeler F, Vaz MA. Effect of light-emitting diodes therapy on knee extensor muscle fatigue. Photomedicine and Laser Surgery. 2010;28(5):653-658. PubMed
- Brondon P, Stadler I, Lanzafame RJ. Melanin density affects photobiomodulation outcomes in cell culture. Photomedicine and Laser Surgery. 2007;25(3):144-149. PubMed
- Bunch J. Photobiomodulation therapeutic lasers: an update and review of current literature. Veterinary Clinics of North America: Small Animal Practice. 2023;53(4):783-799. DOI
- Chung H, Dai T, Sharma SK, Huang YY, Carroll JD, Hamblin MR. The nuts and bolts of low-level laser (light) therapy. Annals of Biomedical Engineering. 2012;40(2):516-533. PubMed Central
- de Freitas LF, Hamblin MR. Proposed mechanisms of photobiomodulation or low-level light therapy. IEEE Journal of Selected Topics in Quantum Electronics. 2016;22(3):7000417. PubMed Central
- Frankowski DW, Ferrucci L, Arany PR, et al. Light buckets and laser beams: mechanisms and applications of photobiomodulation (PBM) therapy. GeroScience. 2025;47(3):2777-2789. PubMed
- Gesuete F, Luciani L, Crotti S, et al. Evaluation of dual-near-infrared-wavelength photobiomodulation therapy for the treatment of canine otitis externa: a prospective multicenter pilot study. Animals. 2026;16(15):2372. Full text
- Giacci MK, Wheeler L, Lovett S, et al. Differential effects of 670 and 830 nm red near infrared irradiation therapy: a comparative study of optic nerve injury, retinal degeneration, traumatic brain and spinal cord injury. PLOS ONE. 2014;9(8). DOI
- Gupta A, Dai T, Hamblin MR. Effect of red and near-infrared wavelengths on low-level laser light therapy-induced healing of partial-thickness dermal abrasion in mice. Lasers in Medical Science. 2014;29(1):257-265. PubMed
- Hale GM, Querry MR. Optical constants of water in the 200-nm to 200-µm wavelength region. Applied Optics. 1973;12(3):555-563. DOI
- Hamblin MR. Mechanisms and applications of the anti-inflammatory effects of photobiomodulation. AIMS Biophysics. 2017;4(3):337-361. PubMed
- Hamblin MR. Mechanisms and mitochondrial redox signaling in photobiomodulation. Photochemistry and Photobiology. 2018;94(2):199-212. PubMed
- Hochman-Elam LN, Heidel RE, Shmalberg JW. Effects of laser power, wavelength, coat length, and coat color on tissue penetration using photobiomodulation in healthy dogs. Canadian Journal of Veterinary Research. 2020;84(2):131-137. PubMed
- Heiskanen V, Hamblin MR. Photobiomodulation: lasers vs. light emitting diodes? Photochemical and Photobiological Sciences. 2018;17(8):1003-1017. DOI
- Huang YY, Chen AC, Carroll JD, Hamblin MR. Biphasic dose response in low level light therapy. Dose-Response. 2009;7(4):358-383. Full text
- Huang YY, Nagata K, Tedford CE, McCarthy T, Hamblin MR. Low-level laser therapy (LLLT) reduces oxidative stress in primary cortical neurons in vitro. Journal of Biophotonics. 2013;6(10):829-838. PubMed
- Ibrahim MM, Patwardhan A, Gilbraith KB, et al. Long-lasting antinociceptive effects of green light in acute and chronic pain in rats. Pain. 2017;158(2):347-360. PubMed Central
- Jacques SL. Optical properties of biological tissues: a review. Physics in Medicine and Biology. 2013;58(11). PubMed
- Jeffery G, Fosbury R, Barrett E, Hogg C, et al. Longer wavelengths in sunlight pass through the human body and have a systemic impact which improves vision. Scientific Reports. 2025;15(1):24435. PubMed
- Jenkins PA, Carroll JD. How to report low-level laser therapy and photomedicine dose and beam parameters in clinical and laboratory studies. Photomedicine and Laser Surgery. 2011;29(12):785-787. PubMed
- Karu TI, Kolyakov SF. Exact action spectra for cellular responses relevant to phototherapy. Photomedicine and Laser Surgery. 2005;23(4):355-361. PubMed
- Kaub L, Schmitz C. More than ninety percent of the light energy emitted by near-infrared laser therapy devices used to treat musculoskeletal disorders is absorbed within the first ten millimeters of biological tissue. Biomedicines. 2022;10(12):3204. DOI
- Kaub L, Schmitz C. Comparison of the penetration depth of 905 nm and 1064 nm laser light in surface layers of biological tissue ex vivo. Biomedicines. 2023;11(5):1355. PubMed Central
- Liebert A, Pang V, Bicknell B, et al. A perspective on the potential of opsins as an integral mechanism of photobiomodulation: It’s not just the eyes. Photobiomodulation, Photomedicine, and Laser Surgery. 2022;40(2):123-135. DOI
- Lima AMCT, Sergio LPS, Fonseca AS. Photobiomodulation via multiple-wavelength radiations. Lasers in Medical Science. 2020;35(2):307-316. DOI
- Martin LF, Patwardhan AM, Jain SV, et al. Evaluation of green light exposure on headache frequency and quality of life in migraine patients: a preliminary one-way cross-over clinical trial. Cephalalgia. 2021;41(2):135-147. PubMed Central
- Millis DL, Bergh A. A systematic literature review of complementary and alternative veterinary medicine: laser therapy. Animals. 2023;13(4):667. DOI
- NASA Science. Tour of the Electromagnetic Spectrum (including “Infrared Waves”). National Aeronautics and Space Administration. NASA
- Prahl S. Tabulated molar extinction coefficient for hemoglobin in water. Oregon Medical Laser Center. OMLC
- Quirk BJ, Whelan HT. What lies at the heart of photobiomodulation: light, cytochrome c oxidase, and nitric oxide—review of the evidence. Photobiomodulation, Photomedicine, and Laser Surgery. 2020;38(9):527-530. PubMed
- Salehpour F, Cassano P, Rouhi N, Hamblin MR, De Taboada L, Farajdokht F, Mahmoudi J. Penetration profiles of visible and near-infrared lasers and light-emitting diode light through the head tissues in animal and human species: a review of literature. Photobiomodulation, Photomedicine, and Laser Surgery. 2019;37(10):581-595. PubMed
- Sarbadhikary P, George BP, Abrahamse H. Paradigm shift in future biophotonics for imaging and therapy: miniature living lasers to cellular scale optoelectronics. Theranostics. 2022;12(17):7335-7350. Figure used under CC BY 4.0. Full text
- Setchfield K, Gorman A, Simpson AHRW, Somekh MG, Wright AJ. Effect of skin color on optical properties and the implications for medical optical technologies: a review. Journal of Biomedical Optics. 2024;29(1):010901. PubMed
- Sommer AP. Mitochondrial cytochrome c oxidase is not the primary acceptor for near infrared light, it is mitochondrial bound water: the principles of low-level light therapy. Annals of Translational Medicine. 2019;7(Suppl 1). DOI
- Souza-Barros L, et al. Skin color and tissue thickness effects on transmittance, reflectance, and skin temperature when using 635 and 808 nm lasers in low intensity therapeutics. Lasers in Surgery and Medicine. 2018;50. DOI
- Tedford CE, DeLapp S, Jacques S, Anders J. Quantitative analysis of transcranial and intraparenchymal light penetration in human cadaver brain tissue. Lasers in Surgery and Medicine. 2015;47(4):312-322. PubMed
- US Environmental Protection Agency. Radiation basics. EPA
- Vatansever F, Hamblin MR. Far infrared radiation (FIR): its biological effects and medical applications. Photonics and Lasers in Medicine. 2012;1(4):255-266. PubMed Central
- Wang Y, Huang YY, Wang Y, Lyu P, Hamblin MR. Red 660 nm or near-infrared 810 nm photobiomodulation stimulates, while blue 415 nm and green 540 nm light inhibit proliferation in human adipose-derived stem cells. Scientific Reports. 2017a;7:7781. DOI
- Wang Y, Huang YY, Wang Y, et al. Photobiomodulation of human adipose-derived stem cells using 810 nm and 980 nm lasers operates via different mechanisms of action. Biochimica et Biophysica Acta – General Subjects. 2017b;1861(2):441-449. PubMed
- Wang Y, Wang Y, Wang Y, Murray CK, Hamblin MR, Hooper DC, Dai T. Antimicrobial blue light inactivation of pathogenic microbes: state of the art. Drug Resistance Updates. 2017c;33-35:1-22. PubMed Central
- Wu Q, Xuan W, Ando T, Xu T, et al. Low-level laser therapy for closed-head traumatic brain injury in mice: effect of different wavelengths. Lasers in Surgery and Medicine. 2012;44(3):218-226. PubMed
- Wunsch A, Matuschka K. A controlled trial to determine the efficacy of red and near-infrared light treatment in patient satisfaction, reduction of fine lines, wrinkles, skin roughness, and intradermal collagen density increase. Photomedicine and Laser Surgery. 2014;32(2):93-100. PubMed Central
- Yadav A, Gupta A. Noninvasive red and near-infrared wavelength-induced photobiomodulation: promoting impaired cutaneous wound healing. Photodermatology, Photoimmunology and Photomedicine. 2017;33(1):4-13. PubMed
Image credits
- Figures 1 and 2: MedcoVet, built from the published data cited in each caption.
- Figure 3: Ash C, Dubec M, Donne K, Bashford T. Lasers in Medical Science. 2017;32(8):1909-1918. Reproduced unmodified under the Creative Commons Attribution 4.0 license.


