
The WAIT Test™ › Average Power
Average Power in Red Light Therapy: What It Means, Why It Matters, and How to Evaluate a Device
On this page
- What is average power in red light therapy?
- Why average power matters (and why it isn’t what most people think)
- Where Average Power fits in The WAIT Test™
- How to evaluate an average-power claim
- The WAIT Test™ standard for Average Power
- Is there one ideal average power for at-home red light therapy?
- Strong disclosure, incomplete disclosure, and warning signs
- Worked example: can the power cover a hip?
- The science: what average power measures
- The essential terms: power, irradiance, energy, and dose
- The core power calculation
- How average power connects to irradiance
- Average optical power is not electrical wattage
- Average power versus peak power
- Why a high total wattage can still produce low irradiance
- Average power is not the dose
- What tissue responds to
- Why more average power is not always better
- Does more power make light go deeper?
- Why contact and fur change the power that reaches a pet
- What veterinary research tells us about power
- Technical details
- Frequently asked questions about average power
- Does more power mean the light reaches deeper?
- Does more power mean shorter treatments?
- What is a good average power for red light therapy?
- Is 1 W a high-power red light device?
- Is average power more important than peak power?
- Can I calculate average power from peak power?
- Is irradiance the same as average power?
- Is energy density the same as power density?
- Can a lower-power device work if I use it longer?
- Does high peak power send light deeper?
- Does a Class IV laser work better than a lower-power device?
- Does a lower laser class mean lower power?
- Is eye safety based on a device’s power?
- How do I know whether a company's power number is real?
- Why does fur matter if the device has enough power?
- Can average power tell me how much light reaches a joint?
- The bottom line
- Continue The WAIT Test™
- Research and references
Here’s a practical question. You’re comparing two red light therapy devices for your pet. One is a 1 Watt device. The other is a 2 Watt device. Which one should you choose?
If you’re trying to get enough light to the target tissue, you’d pick the 2 Watt device, right? After all, more power is better…
Not necessarily.
The same goes for clinical lasers, many of which are rated at 15 to 25 W. Does that make them 25 times better than a 1 Watt home device? Or 25 times faster? No.
To determine which device is better (or if either device is good enough to have a clinical effect), you need the full WAIT Test™, and Average power is a key part of that test.
What is average power in red light therapy?
The quick answer
Average optical power is the amount of therapeutic light a device outputs each second, on average. You’ll see it measured in watts or milliwatts.
- 1 watt = 1,000 milliwatts
- 1 watt = 1 joule per second
- Energy (J) = average power (W) x time (s)
If the device runs steadily, operating power and average power are basically the same thing. But if it pulses, average power accounts for both on- and off-time. That means average power can be way lower than the peak power.
When you’re comparing devices, look for the measured average optical output power during real use. Ignore electrical input, adapter wattage, peak power, diode specs, or how many LEDs are crammed in.
A bigger wattage number doesn’t always mean a better device. What matters is whether the wavelength, average power output, area, time, and delivery method work together to provide safe, effective treatment. That’s the idea behind the WAIT Test.
Why average power matters (and why it isn’t what most people think)
Most people look at a device’s power for two reasons. They want a device strong enough to reach the target, and they’ve heard that more power means shorter treatments. Here’s why the bigger number doesn’t automatically win:
- Reaching the target depends mostly on wavelength. Wavelength decides how much light tissue lets through (Jacques, 2013; Ash et al., 2017). Because transmission is a fraction, more power delivers more total light but doesn’t change the share that reaches the target.
- Treatment time depends on irradiance, not total power. Irradiance is how much power lands on each square centimeter of skin. A 5 W pad spread over a large area can deliver less light per square centimeter than a 1 W probe over a small one. The dose, measured in J/cm², is irradiance multiplied by time.
So why does average power matter? The key word is average.
You need irradiance to calculate dose, and irradiance comes from average power divided by the treatment area. That’s where many companies fall short. Some never report average power. Others report peak power, which, for a pulsed device, can be many times higher than what the device delivers over a session. Either way, you can’t calculate an accurate irradiance or dose.
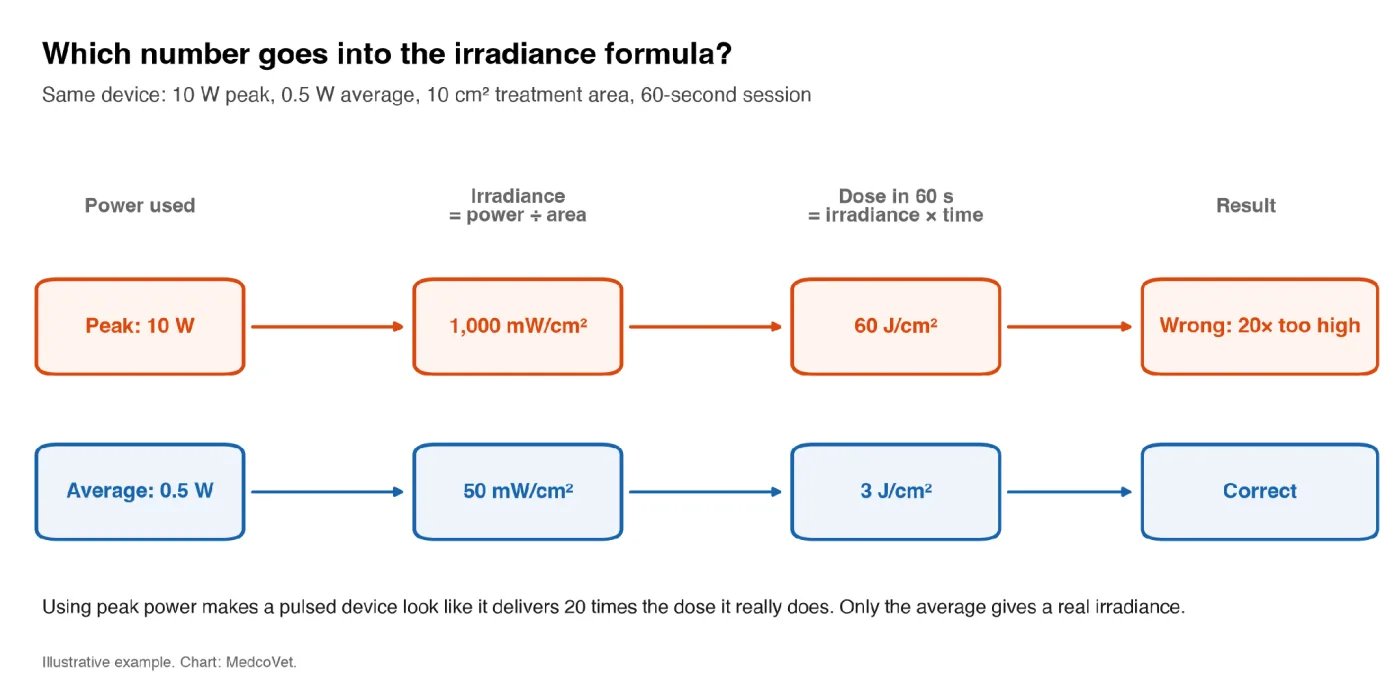
Figure 1. The same pulsed device, calculated two ways. Plugging in peak power instead of average power inflates the irradiance and the dose. Example: 10 W peak at a 5% duty cycle (0.5 W average) over a 10 cm² treatment area. Chart: MedcoVet.
This step of The WAIT Test™ confirms that the most important input to dosage is real before you do any dose math. If you can’t find the measured average optical power, you can’t trust the irradiance, the treatment time, or the dose built on top of it.
The central question is practical:
Does the company report a measured average optical power you can trust, so you can calculate the irradiance and dose for the target tissue?
Where Average Power fits in The WAIT Test™
Red light therapy has one job: get the right kind of light, in the right amount, to the target tissue. That’s why MedcoVet built The WAIT Test™.
The WAIT Test™ checks whether a red light therapy device can deliver a useful dose of light to the tissue that needs it. It has four components, and a device must pass all four:
Wavelengths
Is it the right kind of light for the target tissue?
The device must emit red or near-infrared light in a band that counts for the condition.Read the guide →Average Power
Is there enough light to treat the whole area?
The device’s true average optical output must cover the treatment area in one session.You’re reading this guideIrradiance
Is the light concentrated enough to deliver the dose in time?
The usable light at the skin must deliver the dose at each site within the time limit.Read the guide →Target Tissue
Does the light reach the target tissue?
The light must get past fur and be applied the way the condition needs.Read the guide →Each device is judged separately for each condition and coat, so the same device can pass for a wound and fail for a hip. The full method, including the data you need and the decision rules, is in The WAIT Test™ guide.
This guide covers the second component, Average Power. Passing one component, such as having strong average power, can’t make up for failing another.
This guide starts with how to check a device’s average power, including a worked example. Then it explains what average power measures, and it ends with technical detail on heat, measurement, multi-wavelength devices, and laser class.
How to evaluate an average-power claim
Keep it simple. Four steps, plus an optional fifth:
Step 1: Find the three key numbers
Look on the product page or in the manual for:
- Average power in W or mW
- Irradiance in mW/cm²
- Spot size (treatment area) in cm²
If the average power is missing, that’s already your answer: you can’t calculate irradiance or dose for this device.
Step 2: Make sure it’s optical, average power
The number should be light output, averaged over normal use. Watch for the common tricks: electrical or adapter wattage, LED count multiplied by a component rating, peak power from a pulsed device, or “maximum” startup power. If the spec sheet doesn’t say, ask the company directly whether it’s measured average optical power or a peak value.
If the device pulses, the company should also publish the full pulse details: peak power, pulse width, frequency, and duty cycle. Without them, you can’t check that the average is really an average.
Step 3: Check that the numbers add up
Average power should be roughly the irradiance multiplied by the spot size. For example, 76 mW/cm² over 14.5 cm² is about 1,100 mW, or 1.1 W. If the numbers don’t agree, something in the specification is off.
If the device uses more than one wavelength, ask for the average power at each wavelength, and calculate the irradiance for red and near-infrared separately, since they serve different purposes. For example, 0.4 W of 660 nm red and 0.7 W of 850 nm near-infrared over a 14.5 cm² head works out like this:
| Wavelength | Average power | Irradiance | Dose in 60 s |
|---|---|---|---|
| 660 nm red | 0.4 W | 27.6 mW/cm² | 1.66 J/cm² |
| 850 nm near-infrared | 0.7 W | 48.3 mW/cm² | 2.90 J/cm² |
| Combined | 1.1 W | 75.9 mW/cm² | 4.55 J/cm² |
Step 4: Check that the power can cover the area in time
Multiply the target dose by the treatment area to get the energy you need, then divide by the average power that actually reaches the skin. If the session runs longer than you can realistically keep the device in place on your pet (MedcoVet uses 10 minutes for most joints), the power isn’t enough for that area, however good the other numbers look.
Optional step 5: Ask for a third-party test report
For extra confidence, you can ask the company for an independent, third-party report that measured the device’s output. A useful report shows the measured average power (for each wavelength, if there’s more than one), the irradiance at the skin or treatment distance, and the spot size, along with the instrument and method used. It’s a nice extra, not a requirement. Plenty of good devices are made without one.
Then complete The WAIT Test™
Average power passes only one part of the evaluation. Also confirm:
- Wavelengths: Is it the right kind of light for the target tissue?
- Irradiance: Is the light concentrated enough to deliver the dose in time?
- Target Tissue: Does the light reach the target tissue?
The standard
The WAIT Test™ standard for Average Power
The Average Power component has four checks, worth 30 points in all. Each is scored separately for every condition.
- A1. Average optical power known (10 points). The measured average optical power is known, whether the company publishes it, MedcoVet measures it, or a third party reports it (for example, an FDA summary or a joules table in the manual). Electrical wattage, a component rating, LED count, and peak power don’t count. A power stated as “up to,” or not stated as average, counts only as the best case, so A1 stays open.
- A2. Pulse details known (5 points). A continuous device passes. A pulsed device needs its full pulse details: peak power, pulse duration, frequency, and duty cycle.
- A3. Power known per wavelength (5 points). A multi-wavelength device needs its red/near-infrared split. A single-wavelength device passes.
- A4. Enough power to cover the area in one session (10 points). After fur and coat losses, and counting only near-infrared for a deep target, the power must deliver the condition’s target dose over its whole treatment area within the session limit.
Company specifications, MedcoVet measurements, and third-party sources all count as information. MedcoVet’s current readings come from a solar power meter, which reads LED light high, so each one is scored across a range: the reading ÷ 20 (worst case) to ÷ 13 (best case). That’s an interim measure until the devices are re-measured with a thermopile power meter.
Average Power result
Pass or fail, per condition. A1 and A4 are worth 10 points each, so failing either one fails Average Power. A2 and A3 are worth 5 points each: missing one still passes, but missing both fails.
How The WAIT Test™ scores a device. Each device gets one result for each situation (the condition being treated and the coat over the area), not one result overall. Each check is worth a set number of points, and the checks are grouped under the four components. A device passes only if it clears the eye-safety gate and earns at least 75% of the available points in each of W, A, I, and T. It fails if any component stays below 75% even when every missing figure turns out as favorably as possible. If nothing has failed but a missing figure could still decide the result, it needs more information: it can’t pass until the figure is supplied, but it hasn’t failed either. The score out of 100 ranks devices and never overrides the result; when figures are missing, it’s shown as a range. Class 3B and 4 lasers and Risk Group 2–3 LEDs are not safe for home use and aren’t scored. See how every device does, condition by condition, in The WAIT Test™ Device Scorecard.
If the information isn’t available
If the average power isn’t known from any source, A1 is open rather than failed. The device can’t pass until the figure is supplied, but it hasn’t failed for that alone.
Open figures are worked out at their best and worst case. If the red/near-infrared split isn’t known, the dose math runs from all near-infrared to none. If the head area isn’t known, irradiance and time per site stay open.
A device still fails if A4 can’t be met even in the best case, such as a device whose best-case session for a hip runs past 10 minutes.
The one question to ask
What is the measured average optical power of this device (for each wavelength, if there’s more than one)?
If the company can’t answer and no measurement or third-party figure exists, A1 stays open, and the device can’t pass the Average Power part of The WAIT Test™ until the figure is known.
Is there one ideal average power for at-home red light therapy?
No. A useful average power depends on the complete design and intended use.
Relevant factors include:
- Target tissue and depth
- Wavelength
- Treatment area
- Intended irradiance
- Treatment time
- Continuous or pulsed output
- Contact and distance
- Heat management
- Patient size, skin, and coat
- Treatment frequency
- Supporting clinical protocol
A small applicator may need much less power than a large pad because it covers a smaller area. A bigger applicator may need more power to keep the same average irradiance. A lower-output device can still work if used longer. A higher-power device can work faster, but it needs careful control of irradiance, timing, and temperature.
The goal isn’t to chase the highest wattage. The goal is to have enough measured average optical power to deliver the right exposure over the real treatment area, in a reasonable time, without overheating or unsafe dosing.
That’s what The WAIT Test™ checks in A4. It takes WALT’s target dose for the condition, multiplies it by the treatment area to get the required energy, and divides by the power that reaches the skin. That power is counted after fur and coat losses, and for a deep target only the near-infrared share counts. The answer has to fit within MedcoVet’s practical session limit for treating at home: 10 minutes for most joints, 15 for back and neck, 24 for IVDD, and 30 for wounds.
Here’s how it plays out for a 50 lb dog’s hip. WALT targets about 9 J/cm² over roughly 40 cm², or 360 J. A device that puts 1.3 W of near-infrared on the skin delivers that in about 4.6 minutes and passes. An 83 mW device that sits on top of the fur gets only about a quarter of its light through the coat, roughly 21 mW, so it would need close to 5 hours. That’s not a treatment anyone can do at home.
Strong disclosure, incomplete disclosure, and warning signs
Strong average-power disclosure
Average power: 1.1 W (0.4 W at 660 nm, 0.7 W at 850 nm). Irradiance: 76 mW/cm² at the skin. Spot size: 14.5 cm². Measured by an independent lab; report available on request.
The average power is optical and split by wavelength, and the numbers add up (76 mW/cm² × 14.5 cm² ≈ 1.1 W). The third-party report is a bonus.
Incomplete disclosure
Power: 10 W.
There’s no way to tell if that’s optical or electrical, average or peak, and there’s no irradiance, spot size, or report to check it against.
Warning signs
Be cautious when a company:
- Doesn’t list average power, irradiance, or spot size
- Lists numbers that don’t add up
- Quotes peak power, electrical wattage, or LED count instead of measured average optical power
- Gives one combined number for a multi-wavelength device with no breakdown
- Claims that higher wattage automatically means deeper or better treatment
Worked example
Worked example: can the power cover a hip?
Here’s how the Average Power checks play out for five devices in The WAIT Test™ device comparison, for a 50 lb dog’s hip under a light coat. The hip needs 9 J/cm² over about 40 cm² within a 10-minute session.
| Device | Average power (source) | Pulse details (A2) | Per wavelength (A3) | Hip session (A4) | Average Power |
|---|---|---|---|---|---|
| MedcoVet Luma | 1,300 mW (published) | Continuous | Yes | 4.6 min | 100%: pass |
| B-Cure Laser Vet Pro | 83 mW (from 5.0 J per minute) | Pulsed, full details | Single wavelength | 289 min | 67%: fail |
| Yugo Pets Red Light Therapy Device | 77 mW (from its FDA summary) | Continuous | Yes | 2,000 min | 67%: fail |
| Illumi-Vet 3000 | 500 mW (published) | Continuous | Split not published | At least 48 min | 50–67%: fail |
| Ortho Pawz Companion Wrap | Not known | Not known | Split not published | Can’t be worked out | 0–100%: need more info |
The B-Cure and Yugo show that a figure from any reliable source counts: the Yugo’s 77 mW comes from its FDA summary. Both still fail A4, because that little power can’t cover a hip in a practical session once the coat takes its share. The Illumi-Vet’s red/near-infrared split isn’t published, but even if all 500 mW were near-infrared, its best-case session runs past 48 minutes, so it fails anyway. The Ortho Pawz wrap has no known power at all, so every Average Power check is open: it needs more information, not a fail.
The same rules apply to our own device. Under a dark coat, the Luma needs about 14 minutes for the hip, past the 10-minute limit, so it fails Average Power in that situation.
Deep dive
The science: what average power measures
The essential terms: power, irradiance, energy, and dose
PBM product pages often use the word “power” to refer to several different measurements. They are related, but they are not interchangeable.
| Term | Unit | What it tells you | What it does not tell you |
|---|---|---|---|
| Average optical power | W or mW | Average rate of optical energy output | How concentrated the light is or how much reaches a deep target |
| Peak optical power | W or mW | Highest instantaneous power during a pulse | Total energy emitted during treatment |
| Pulse energy | J or mJ | Energy in one pulse | Total session energy without pulse frequency and time |
| Irradiance | W/cm² or mW/cm² | Optical power arriving per unit area | Total energy without treatment time |
| Radiant energy | J | Total optical energy emitted or delivered | How that energy is distributed across an area |
| Radiant exposure | J/cm² | Energy delivered per unit area | How quickly it was delivered or how much reached depth |
| Electrical input power | W | Electricity consumed by the device | Therapeutic optical output |
Researchers have warned for years that missing parameters, terminology errors, and unverified output make PBM studies difficult or impossible to reproduce. Jenkins and Carroll identified wavelength, power, time, beam area at the treatment surface, and pulse parameters among the minimum information needed for a repeatable study. Hadis and colleagues reviewed 74 PBM papers and found that 41% did not report power, 40% did not report beam area, 43% did not report irradiance, and 73% did not explain how the light was measured. A 2025 proposed reporting framework noted that missing data and unverified specifications remain problems in laser research (Jenkins and Carroll, 2011; Hadis et al., 2016; Shurrab, 2025).
These aren’t just paperwork slip-ups. If the power or area is off, every calculation that depends on them is off too.
The core power calculation
Power is energy per unit time:
Energy (J) = average power (W) x treatment time (s)
Examples:
| Average power | Time | Energy |
|---|---|---|
| 0.05 W | 60 s | 3 J |
| 0.10 W | 60 s | 6 J |
| 0.50 W | 60 s | 30 J |
| 1.00 W | 60 s | 60 J |
| 1.00 W | 30 s | 30 J |
This math answers a simple but crucial question: how much optical energy did the device actually deliver across the measured area during the session?
But it doesn’t tell you how that energy is spread out. A 1 W probe over 1 cm² and a 1 W pad over 100 cm² both put out the same total power, but their average irradiance is worlds apart.
How average power connects to irradiance
If optical power is distributed uniformly across a known area, average irradiance can be estimated as:
Average irradiance (W/cm²) = average power (W) / treatment area (cm²)
Radiant exposure can then be calculated as:
Radiant exposure (J/cm²) = average irradiance (W/cm²) x time (s)
Notice what both formulas start with: average power. If that number is missing, or if it’s really a peak value, everything calculated from it is wrong.
Average optical power is not electrical wattage
You might see wattage listed for the power adapter, battery, LED chips, or just electrical use. None of those numbers tell you how much optical power the device actually puts out.
Electrical energy is divided among several paths:
- Light output at different wavelengths
- Heat generated in the emitters
- Driver circuitry
- Control electronics
- Fans, displays, and other components
- Conversion losses
A 20 W adapter does not mean the device gives 20 W of optical power. Similarly, 100 LEDs rated at 1 W each do not add up to 100 W of light output. LEDs may run below their rating; they aren’t 100% efficient, and some light may not reach the treatment area.
Look for wording such as:
Measured average optical output power: 1.1 W at the treatment surface during the standard operating mode.
Be careful with vague labels like “device power,” “total wattage,” “maximum power,” or “100 W LED system.” These are incomplete unless the manufacturer explains exactly what was measured.
Average power versus peak power
Peak power is the maximum light energy produced at any single moment within a pulse. In contrast, average power is calculated over a set period of time, factoring in both the times when the light is on and when it is off or emitting less.
For a stable continuous-wave source:
Average power is approximately equal to operating power.
For an ideal rectangular pulsed source:
Average power = peak power x duty cycle
Duty cycle is the fraction of time the source is on. A 10 W pulse operating at a 1% duty cycle has an average power of:
10 W x 0.01 = 0.10 W
Over 60 seconds, its total energy is:
0.10 W x 60 s = 6 J
Reporting only “10 W peak power” would make the output appear 100 times greater than the average power used to calculate session energy. Plugging that peak number into the irradiance formula would make the dose you calculate 100 times too high.
Here’s what that looks like with a second example, a 10 W peak at a 5% duty cycle:
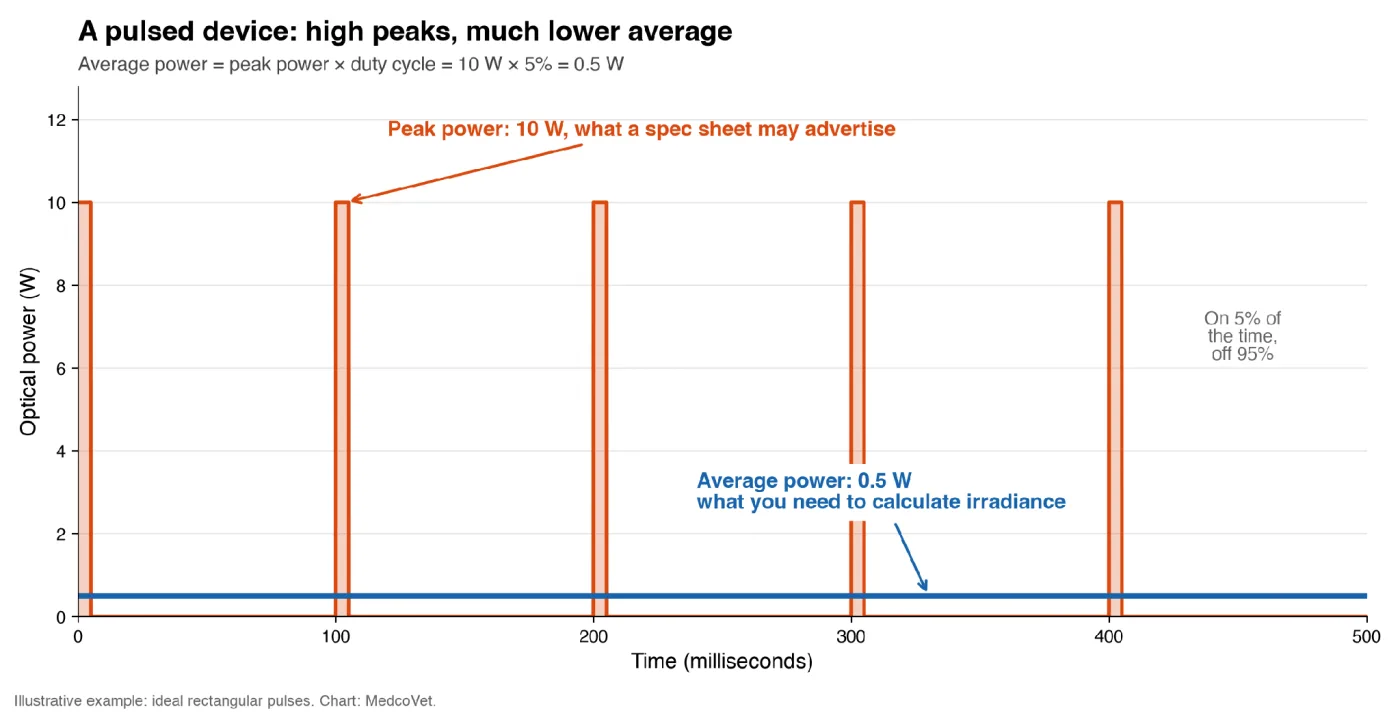
Figure 2. A pulsed device spends most of its time off. The peaks reach 10 W, but the average, the number that goes into irradiance and dose, is only 0.5 W. Chart: MedcoVet.
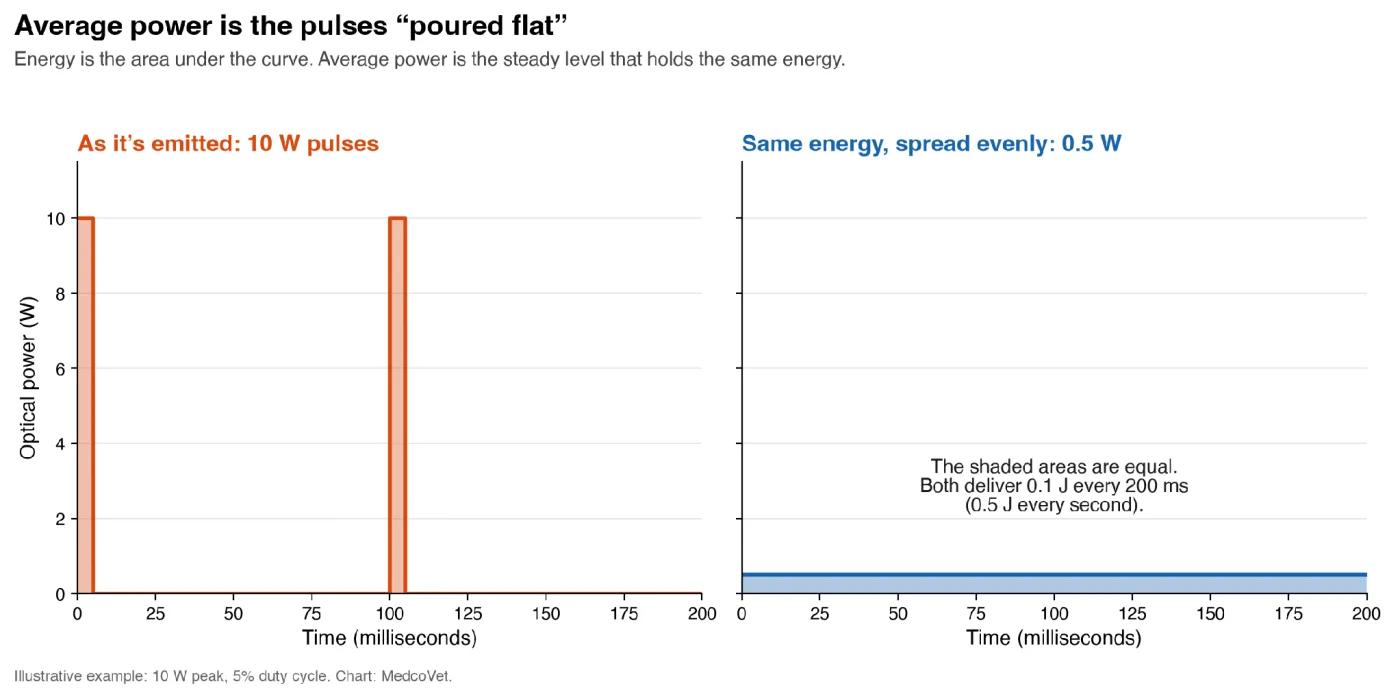
Figure 3. Average power is the steady level that delivers the same energy as the pulses. The two shaded areas are equal. Chart: MedcoVet.
For a pulse train, average power can also be calculated from pulse energy:
Average power = energy per pulse x pulse frequency
The basic peak-power calculation is accurate only if you know the pulse shape and duty cycle precisely. In practice, pulses can vary in height and duration, or include complex waveforms. Therefore, measuring the average power over time gives a more dependable result than relying on theoretical calculations.
Does peak power matter?
Yes, but peak power tells you something different.
Peak power, pulse duration, frequency, duty cycle, and energy per pulse describe how the exposure is arranged in time. Pulse structure can affect thermal behavior and may affect biological response. A review of pulsed PBM found examples favoring pulsed delivery, examples favoring continuous delivery, and many conditions where evidence was insufficient to choose one mode (Hashmi et al., 2010). Pulse parameters were also reported poorly and inconsistently.
In a mouse traumatic brain injury study, researchers delivered continuous 810 nm light and 810 nm light pulsed at 10 Hz or 100 Hz with the same average irradiance and total fluence. Outcomes differed, with the 10 Hz group showing better recovery on the reported measure at 28 days (Ando et al., 2011). This animal study used one injury model. It does not identify a universal pulse frequency, but it shows why average power and total energy do not fully describe a pulsed exposure.
In another experiment, a 200 mW continuous 810 nm laser and a 60 mW superpulsed 904 nm laser showed different transmission profiles through isolated rat skin (Joensen et al., 2012). The devices differed in wavelength, power, and pulse structure, so the result cannot prove that pulsing alone caused the difference. It does show that you can’t interpret a peak-power claim without the other device parameters.
The correct conclusion is:
- Peak power is relevant to pulse behavior.
- Average power is required to calculate total energy over time.
- Neither number proves clinical effectiveness on its own.
- A pulsed device should disclose both, along with the complete pulse settings.
Continuous, pulsed, and superpulsed output
| Mode | What it means | What the company should report |
|---|---|---|
| Continuous wave | Stays on at a relatively steady level | Measured average power and output stability |
| Gated or pulsed | Switches on and off at a stated pattern | Average power, peak power, pulse width, frequency, duty cycle, and pulse energy |
| Superpulsed | Produces very short pulses that may have high peaks but modest average output | The same pulse data, plus measured average power in the treatment mode |
Superpulsed just tells you how the device operates, not how well it works. A device can have sky-high peak power and still deliver low average output.
Why a high total wattage can still produce low irradiance
Total power must be read with the treatment area.
Consider two simplified devices:
| Device | Average power | Treatment area | Average irradiance |
|---|---|---|---|
| Small probe | 1 W | 2 cm² | 500 mW/cm² |
| Large pad | 5 W | 100 cm² | 50 mW/cm² |
The pad has five times the total power, but the probe has ten times the area-average irradiance. Neither comparison says which device is appropriate. The probe may treat a small point quickly and may require careful thermal control. The pad may cover a broad area more evenly and take longer. That’s why you can’t just compare devices of different sizes by total wattage. Average power tells you the total output rate. Irradiance tells you how concentrated that output is at the treatment surface.
Average power is not the dose
The word “dose” is often used loosely in PBM. It may refer to total energy, energy per area, energy at the surface, estimated energy at depth, or an entire treatment schedule. This ambiguity has long been identified as a barrier to comparing PBM protocols (Enwemeka, 2009).
Average power is one input to dose calculation, and everything else is built on it. A complete exposure description includes at least:
- Average power
- Treatment time
- Treatment area
- Irradiance
- Radiant exposure
- Wavelength
- Pulse mode
- Number of treatment points
- Number and spacing of sessions
- Placement and contact
Two devices can emit the same total energy and still deliver very different exposures. For example, 0.5 W for 60 seconds and 1 W for 30 seconds both equal 30 J. The second device delivers that energy twice as quickly. If the treatment areas are equal, it also has twice the irradiance.
The biological effects will differ. PBM doesn’t reliably follow reciprocity, the simple rule that swapping power and time gives the same result.
What tissue responds to
Tissue does not respond to a wattage label. A photobiological response begins when molecules in cells and tissue absorb photons of suitable wavelengths. Proposed PBM mechanisms include changes in mitochondrial activity, nitric oxide signaling, reactive oxygen species, calcium signaling, gene expression, and inflammatory pathways. Active pathways can vary by wavelength, cell state, and exposure conditions (de Freitas and Hamblin, 2016).
Average power matters because it is the source term for the exposure, but the tissue experiences something more specific:
- The device emits optical power.
- That power spreads over an area, producing irradiance.
- Skin, fur, blood, fat, and other tissue reduce and redistribute light.
- A fraction reaches the target tissue.
- Relevant molecules absorb a fraction of the arriving light.
- The absorbed exposure can initiate a biological response.
That’s why saying average power drives healing is way too broad. Average power tells you what’s available to deliver. But it’s irradiance, wavelength, tissue transmission, absorption, time, and the biological state that decide what actually reaches the target tissue.
That’s also why two products with the same wattage can act totally differently. One might spread light over a bigger area. Another might lose more light before it even hits the skin. Some split output across different wavelengths. Some have a hot spot in the middle and weak edges. The number on the label is just the start.
Why the same joules delivered at different rates don’t give the same result (reciprocity) is explained in the Irradiance guide.
Why more average power is not always better
Higher average power can speed up treatments by delivering the same energy in less time. That can help, and it might make it easier to keep the device in place since the session is shorter. A 2026 network meta-analysis of 22 randomized trials (1,353 patients) found that high-intensity lasers reduced pain somewhat more than low-level lasers in some comparisons, but the differences were “generally modest and frequently below” the smallest change patients would notice (de la Barra Ortiz et al., 2026).
But increasing power can also:
- Raise irradiance when area stays constant
- Increase skin temperature
- Make timing errors more important
- Increase the effect of beam hot spots
- Deliver an excessive surface exposure before enough light reaches a deep target
- Move the exposure outside the range used in supporting research
PBM often has a biphasic response. Too little light may not help, and more light can help up to a certain point. After that, more light may not help or could even reduce the effect. Studies have found these patterns in several PBM models (Huang et al., 2011; Sharma et al., 2011). This does not create one universal maximum power or irradiance. The useful range changes with wavelength, tissue, outcome, treatment area, time, and schedule. Claims such as “all PBM should stay below 300 mW/cm²” or “4 to 8 J/cm² works for most conditions” are too broad to serve as general rules. The first is an irradiance claim, not an average-power claim, and the second ignores the target tissue and protocol.
Does more power make light go deeper?
Power and light penetration are related, but marketing often makes this connection seem simpler than it is. Increasing the device’s power at a constant wavelength and setup increases the total amount of light reaching deeper tissues, but it doesn’t change how much of that light tissue actually lets through. For example, if only 1% of light passes through a tissue, doubling the surface power roughly doubles the amount at depth, but the penetration percentage stays the same. The device must still deal with the other 99% of light, which is mostly absorbed or scattered near the surface and can lead to extra heat in those upper layers.
The percentage that gets through is set mostly by wavelength and the tissue in the way. That’s why wavelength, not power, is the first thing to check for reaching a deep target.
Double the power, up to about 10% deeper
So how much deeper does extra power get you? Not much. Physicist Lars Hode puts it simply: twice the power does not mean twice as deep, but maybe 5 to 10% deeper (Hode).
His example: a 100 mW laser reaches a certain intensity at 10 mm. Drive the same laser at 200 mW, and that intensity shows up at 10.5 to 11 mm. At 400 mW, it moves to 11 to 12 mm (Hode).
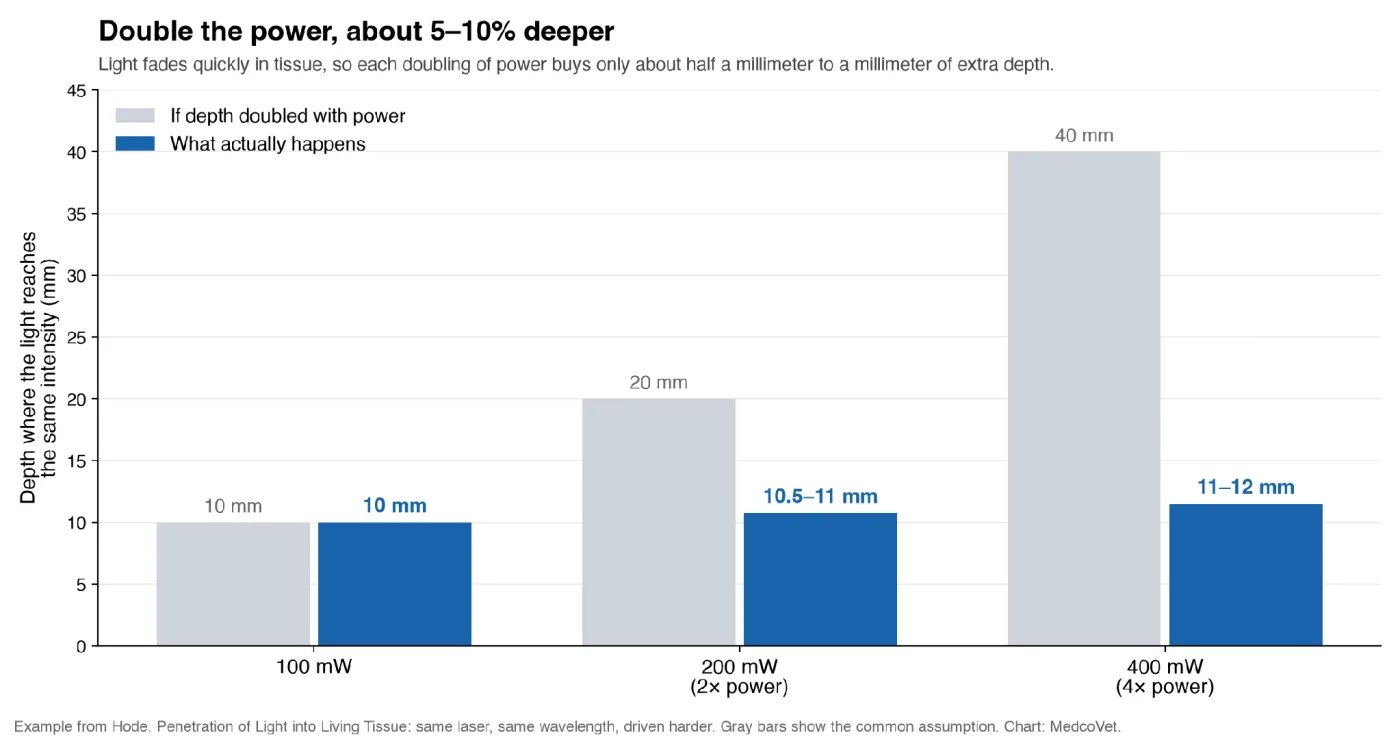
Figure 4. Doubling a laser’s power moves a given light intensity only about half a millimeter to a millimeter deeper. Example from Hode, Penetration of Light into Living Tissue. Chart: MedcoVet.
Why so little? Light fades fast in tissue. Every few millimeters, scattering and absorption take away a large share of what’s left. Doubling the power only buys back one of those steps. So at the same wavelength and setup, a 2 W device isn’t reaching twice as deep as a 1 W device. It reaches roughly a millimeter deeper while putting twice as much light into the surface layers, where most of it is absorbed.
Compare that with wavelength. In Hode’s analysis of light passing through a human hand, 810 nm light got through about 25 times better than 980 nm light. Contact and pressure matter too: pressing the probe into the skin pushes blood out of the light’s path, and skin pigment can absorb much of the incoming light (Hode).
What about high peak power?
Peak power tells a different, more complicated story. Lasers that fire very short, very intense pulses (superpulsing, typical of 904 nm lasers) appear to get through skin more easily. A systematic review assumed in its dose model that the skin removes about 80% of the energy from continuous 820 nm and Nd:YAG (1060 nm) lasers, but only about 50% from pulsed 904 nm GaAs lasers (Bjordal et al., 2003). In a rat skin study, the percentage of light that got through stayed at about 20% with a continuous 810 nm laser, but rose from 38% to 58% over 150 seconds with a superpulsed 904 nm laser (Joensen et al., 2012). One proposed explanation is that the intense pulses temporarily “bleach” the tissue, making it more transparent (Hode).
Two cautions before you go shopping for peak power:
- A higher percentage isn’t “more light”. In that rat study, the continuous laser put out 200 mW and the superpulsed laser 60 mW (average). Twenty percent of 200 mW is about 40 mW through the skin. Even 58% of 60 mW is only about 35 mW. The continuous laser still delivered at least as much light. (This is our rough comparison of absolute output. The authors concluded that the superpulsed laser penetrated two to three times more effectively, and the two lasers also differed in probe design and skin compression.)
- Peak power doesn’t change the dose math. The energy delivered from a pulsed laser is always the average power multiplied by time (Tunér, Hode, and Jenkins). And simple pulsing, which just switches a continuous beam on and off, doesn’t improve penetration (Hode). It only lowers the average power.
The takeaway: more power, peak or average, buys a little extra depth. Wavelength, contact, and pressure buy a lot more. And average power is still the number you need to calculate the dose.
Depth also depends on:
- Wavelength and spectral bandwidth
- Beam diameter and divergence
- Tissue water, blood, fat, and pigment
- Skin and coat characteristics
- Contact angle and pressure
- Continuous or pulsed operation
In healthy dogs, an in vivo transmission study found that power, wavelength, coat color, and shaving all affected the light measured through tissue (Hochman-Elam et al., 2020). An equine skin study found that the lower-average-power device tested transmitted more energy than the Class IV device used for comparison (Luna et al., 2020). This does not mean lower power always penetrates farther. It means total wattage and laser class did not predict transmission across two devices with different wavelengths, pulse designs, applicators, and operating methods.
Average power is just one piece of the puzzle for getting light through tissue. You still need to know how the tissue itself affects the light.
Why contact and fur change the power that reaches a pet
Average output measured in open air is not necessarily the output that reaches the skin during treatment.
How fur, distance, and contact cut the light that reaches the skin is covered in the Target Tissue guide. The WAIT Test™ counts only 25% of a device’s light if it doesn’t part the fur, and that reduced power is what A4 uses.
What veterinary research tells us about power
Veterinary PBM research supports careful parameter reporting, but it does not identify one ideal average power for every animal or condition.
A 2023 systematic review included 45 veterinary laser-therapy studies: 24 in dogs, one in cats, and the remainder in horses. Results conflicted, clinical application was often unclear, and the authors linked some of the uncertainty to wide variation in wavelength, laser class, dose, frequency, and treatment duration. Many studies also carried moderate or high risk of bias (Millis and Bergh, 2023).
Some individual studies show why complete dosing information matters:
- A randomized, blinded, placebo-controlled study in dogs with elbow osteoarthritis used 10 to 20 J/cm² per joint twice weekly for six weeks and reported improvements in lameness and pain measures (Looney et al., 2018). The result supports that this specific protocol worked better than sham in a small trial.
- The healthy-dog transmission study showed that power, wavelength, coat color, and shaving each independently affected transmission (Hochman-Elam et al., 2020).
- The equine skin comparison found that the tested device with lower average power transmitted more energy than the tested higher-power Class IV device, showing that device architecture and delivery method can outweigh total wattage in a head-to-head comparison (Luna et al., 2020).
The straightforward conclusion is that average power is necessary for evaluating a protocol, but it is not independent proof of efficacy. Evidence must match the animal, condition, target tissue, device, and treatment settings.
Technical reference
Technical details
Average power and thermal safety
PBM is supposed to work by light, not by heat. But not every device or setting avoids heating up the tissue.
Temperature rise depends on more than total power:
- Irradiance
- Wavelength
- Exposure time
- Spot size and beam profile
- Tissue absorption
- Skin and coat pigmentation
- Contact and pressure
- Whether the applicator is stationary or moving
- Cooling and heat dissipation
An in vitro investigation of high-energy PBM settings recorded clinically relevant temperature increases under several tested conditions and found that wavelength, applicator size, and movement affected heating (Cronshaw et al., 2023). The study does not set a universal safety threshold for pets or at-home devices. It supports measuring temperature under actual operating conditions rather than assuming a PBM label guarantees non-thermal delivery.
A good at-home device should make it tough to mess up the protocol. Look for features like these:
- Fixed or bounded treatment times
- Stable contact geometry
- Output limits appropriate to the treatment area
- Temperature testing under worst-case normal use
- Clear instructions for skin, coat, and wound use
- Automatic shutoff
- Eye-safety instructions suited to the source
If a pet shows discomfort or the treatment area becomes hot, stop treatment and follow the device instructions or veterinary guidance.
Why measured average power matters
A spec is only useful if it tells you what the device actually puts out.
Hadis and colleagues explain why radiometry for LEDs and lasers requires suitable, calibrated detectors; attention to wavelength response; complete beam capture; geometry; and clear reporting of the measurement method (Hadis et al., 2016). A detector can under- or over-read if the source is too large, the angle is wrong, part of the beam misses the sensor, or the instrument isn’t appropriate for the wavelength and power range.
A common example is the inexpensive “solar power meter.” These meters are calibrated for sunlight, and a detector’s response changes with wavelength, so they can misread narrow-band red and near-infrared light (Hadis et al., 2016). In one light-panel company’s comparison against a reference lab, a solar meter read three panels 31% to 88% too high (GembaRed).
In 2022, Girasol and colleagues measured 24 PBM laser devices in clinical use. Only nine produced average power within 90% to 110% of the manufacturer’s value. Across all devices, measured power ranged from 2% to 134% of the stated value. Beam diameters also differed substantially from the nominal values, and some devices changed output between one and three minutes (Girasol et al., 2022).
That research looked at older clinical laser devices, not newer consumer LED models, so the reported failure rates may not apply to all products. The important point is that the numbers listed on a device’s label do not always match what is actually measured in practice.
What a useful measurement statement should include
A manufacturer should be able to state:
- What was measured: optical power, not electrical input.
- Where it was measured: at the aperture, at a stated distance, or at the skin-contact plane.
- Which mode was measured: continuous, pulsed, red only, near-infrared only, or combined.
- How long the output was sampled: long enough to represent the treatment session.
- Which instrument was used: a detector suitable for the wavelengths and power range.
- Calibration status: when and how the instrument was calibrated.
- How the full beam was captured: especially for large pads, clusters, or divergent LEDs.
- Expected tolerance: unit-to-unit and operating variation.
Independent testing adds confidence, but a named laboratory alone is not enough. The method and operating conditions still matter.
Output stability across the full session
“Maximum power” at startup may not represent average power during treatment.
LED and laser output may fluctuate because of component warming, battery drain, temperature regulation by electronics, or shifts in pulsed program phases. To be accurate, measure average power over the actual treatment session or another well-defined relevant period.
Questions to ask include:
- Is the stated value an initial reading, a maximum reading, or a time average?
- Was the device tested from a fully and partly discharged battery?
- Does output fall when the device warms?
- Do different intensity modes have separate measured values?
- Is the same average power maintained for the full recommended session?
- Does automatic thermal control reduce output, and if so, by how much?
This is important when treatment time is based on the stated power. If output drops by 30% during a session, the energy delivered will be less than you would expect based on the starting value.
What about devices with more than one wavelength?
A multi-wavelength device should disclose how its average output is divided.
Suppose three devices all claim 1 W of total average power at 660 and 850 nm:
| Device | 660 nm output | 850 nm output | Total |
|---|---|---|---|
| A | 0.5 W | 0.5 W | 1.0 W |
| B | 0.8 W | 0.2 W | 1.0 W |
| C | Not disclosed | Not disclosed | 1.0 W |
The three labels do not describe the same information. Devices A and B distribute optical energy differently. Device C prevents the reader from calculating energy at either wavelength.
Ask:
- Do both wavelengths operate at the same time?
- Is the stated power combined or per wavelength?
- What is the measured average power of each wavelength channel?
- Does selecting one wavelength change total output?
- Does pulse mode apply to both wavelengths in the same way?
- Were the channels measured separately with a wavelength-appropriate detector?
For an LED array, also ask whether the measured total includes the full treatment area or is an extrapolation from one emitter.
Laser class is about eye safety, not power or effectiveness
Many websites and product pages treat laser class as a power rating: for continuous-wave lasers, roughly up to 500 mW is Class 3B and over 500 mW is Class 4, and a higher class means a stronger, deeper-reaching, better device. Many also suggest that a device’s eye safety depends on its total power.
Neither is true.
Laser classification is a hazard rating. It describes how much laser light a person could get into their eye and, for Class 3B and 4, onto their skin, from the device (FDA). As Tunér, Hode, and Jenkins put it, laser classification “has nothing at all to do with suitability for laser treatment” (Tunér, Hode, and Jenkins).
What actually decides the class
The international standard, IEC 60825-1, classifies a laser product by the light that can actually reach the eye during use, not by the device’s total output (IEC 60825-1:2014). That depends on:
- Wavelength. Near-infrared light is invisible, so it doesn’t trigger the blink reflex that helps protect the eye from bright visible light.
- Power per emitter that can enter the eye. The test measures light through an opening about the size of a fully open pupil (7 mm), not the device’s combined output.
- Beam divergence and apparent source size. A tight, parallel beam can focus to a tiny, intense spot on the retina. Light that spreads out, or comes from a larger apparent source, is far less concentrated.
- Number and spacing of emitters. Emitters spaced far enough apart can’t all send light into the same pupil at once.
- Exposure time and pulsing.
- Enclosure. Light that can’t get out can’t reach an eye.
Source size alone makes a big difference. Under the standard’s limits for 808 nm near-infrared light, a point-like laser beam can deliver only about 0.6 mW through that pupil-sized opening and still be Class 1. A source that looks large to the eye can deliver about 42 mW through the same opening and still be Class 1. That’s roughly 65 times more light at the same wavelength, in the same class (IEC 60825-1:2014).
Same power, different class
Tunér, Hode, and Jenkins give a clear example. The 500 mW line people quote is the upper limit for Class 3B, so a single continuous laser just over 500 mW is Class 4. Now picture a probe with 10 laser diodes of 450 mW each, placed some distance apart. Each diode is under the limit, so the instrument is Class 3B, even though its total output is 4.5 W (the final class depends on formal testing) (Tunér, Hode, and Jenkins).
| Device | Emitters | Power per emitter | Total output | Typical class |
|---|---|---|---|---|
| A: single laser | 1 | Just over 500 mW | About 0.5 W | Class 4 (over the 500 mW Class 3B limit) |
| B: ten-laser probe | 10, spaced apart | 450 mW | 4.5 W | Class 3B (each emitter under 500 mW) |
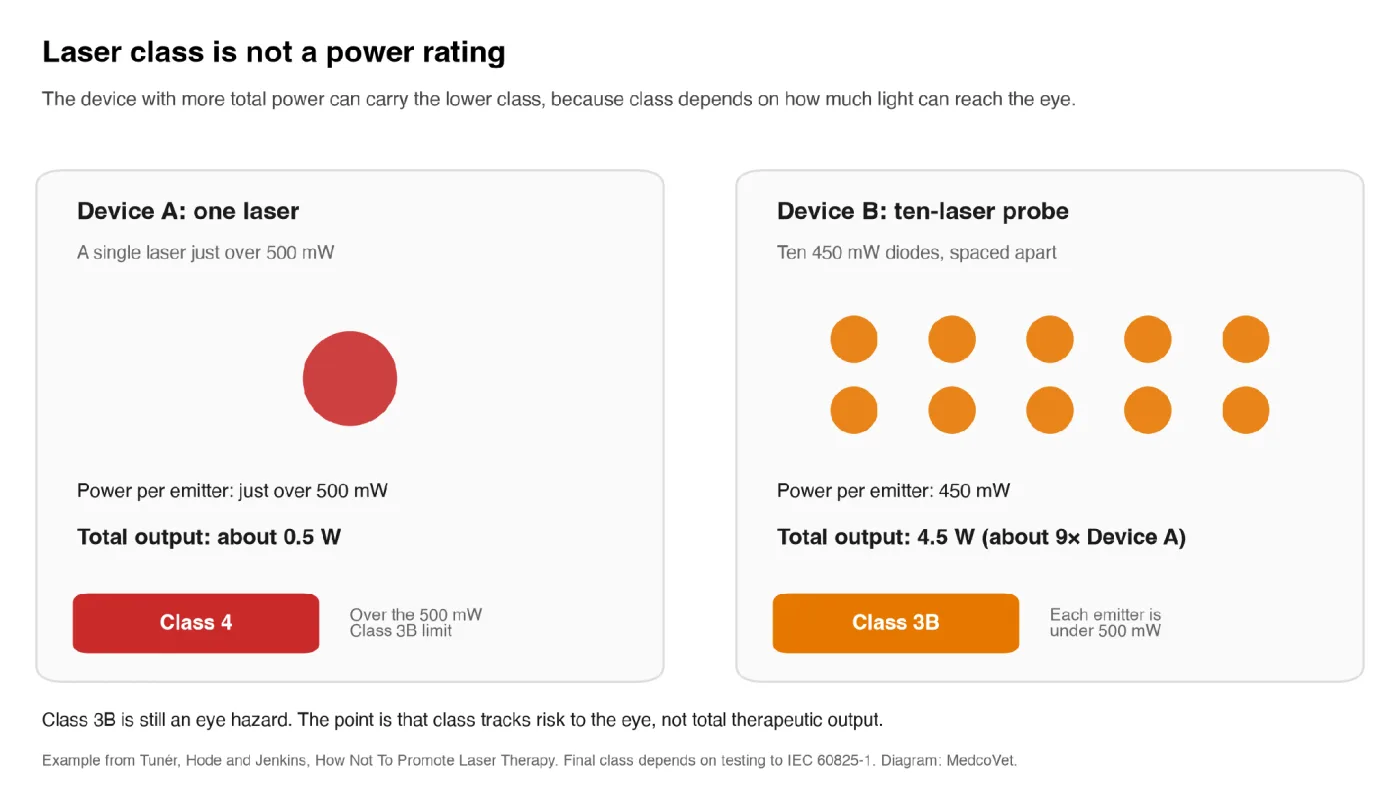
Figure 5. Device B puts out about nine times more total power than Device A but carries the lower class, because class depends on how much light can reach the eye from one emitter, not on the device’s total output. Example from Tunér, Hode, and Jenkins; the final class depends on formal testing. Diagram: MedcoVet.
Device B puts out about nine times more power than Device A, yet carries the lower class. As Tunér, Hode, and Jenkins put it, high power doesn’t mean a laser instrument has to be Class 4.
One caution: a lower class isn’t the same as eye-safe. The FDA describes Class 3B lasers as an immediate eye hazard when viewed directly (FDA). The point isn’t that Device B is safe to look into. The class number doesn’t tell you how much power a device delivers.
Class 1 devices can out-power Class 4 lasers
It goes further than that. “Actually, there are Class I lasers that are higher powered than many Class IV instruments!” (Tunér, Hode, and Jenkins).
That isn’t a loophole. Many Class 1 products, such as enclosed industrial laser systems, contain a Class 3B or Class 4 laser inside a housing that keeps the beam from reaching anyone’s eyes during normal use (CSUS Laser Safety Manual). And a therapy device that spreads its light widely, so only a small fraction can enter the eye at once, can carry a low class despite a high total output.
LED devices are a separate case. LEDs are no longer classified under the laser standard. Their eye and skin safety is assessed under a different standard for lamps and LEDs (IEC 62471), which uses risk groups instead of laser classes.
Class doesn’t predict effectiveness or penetration either
There is no such thing as “Class IV technology.” Choosing an emitter above 500 mW is not a different technology. Apart from power, the only differences between Class 3B and Class 4 lasers are the potential hazards and, usually, the price (Tunér, Hode, and Jenkins).
Higher class doesn’t mean deeper penetration, either. Tunér, Hode, and Jenkins point out that a high-power Class 4 laser at 980 nm can penetrate less than a 500 mW Class 3B laser at 808 nm, because water absorbs more of the 980 nm light near the surface. The extra power mostly becomes heat (Tunér, Hode, and Jenkins). A lower-power device held in contact with slight pressure can get more of its light into the tissue (Tunér, Hode, and Jenkins).
A Class 4 laser can have high average output. Still, the class label does not tell you the wavelength match, beam area, irradiance, pulse structure, treatment time, tissue transmission, or evidence for a condition. Check the real optical measurements, and follow the eye-safety instructions for the specific device. Don’t assume a higher class, bigger wattage, or the word “professional” means better PBM, and don’t assume a lower class means lower power.
That’s also why The WAIT Test™ uses class only as a safety gate, never as a score. A device sold for home use must be eye-safe without goggles. Class 3B and 4 lasers and LEDs in Risk Group 2 or 3 under IEC 62471 are marked Not safe for home use and aren’t scored. A laser with no published class needs more information until its class is published. Devices that clear the gate are then judged on their measured output, like every other device.
Does average power mean the same thing for lasers and LEDs?
The unit is the same. One watt of measured optical power is one joule per second whether the source is a laser or an LED.
The delivery can still differ because lasers and LEDs may have different:
- Beam profiles
- Divergence
- Treatment areas
- Coherence and spectral bandwidth
- Contact methods
- Pulse structures
- Power distribution across the treatment plane
Research standards apply to both lasers and LEDs. A study on lasers doesn’t automatically prove an LED product works, and vice versa. The device and protocol have to be close enough for the evidence to count.
FAQ
Frequently asked questions about average power
Does more power mean the light reaches deeper?
Not in the way most people think. More power sends more total light in, but wavelength and the tissue in the way mostly determine what fraction reaches a deep target. Wavelength is the first thing to check for depth.
Does more power mean shorter treatments?
Only if the treatment area stays the same. Treatment time depends on irradiance, which is average power divided by area. A high-wattage device spread over a large pad can need longer sessions than a low-wattage probe.
What is a good average power for red light therapy?
There’s no magic number. The right output depends on treatment area, irradiance, time, wavelength, pulse mode, target tissue, and thermal control. Look for a complete, well-documented protocol, not just a big wattage.
Is 1 W a high-power red light device?
It depends on the area. One watt over 1 cm² is very different from one watt over 100 cm². Output mode and treatment time matter too.
Is average power more important than peak power?
Average power is the essential value for calculating total energy, irradiance, and dose. Peak power is important for describing a pulse. A complete pulsed-device specification needs both.
Can I calculate average power from peak power?
For ideal rectangular pulses, multiply peak power by duty cycle. For example, 10 W at a 1% duty cycle averages 0.1 W. Real pulse shapes may be more complex, so measured average power is preferable.
Is irradiance the same as average power?
No. Average power is total optical output in W or mW. Irradiance is optical power per unit area in W/cm² or mW/cm². You need average power to calculate irradiance.
Is energy density the same as power density?
No. Power density is a common name for irradiance and is measured in W/cm². Energy density is a common name for radiant exposure and is measured in J/cm². Time connects them.
Can a lower-power device work if I use it longer?
It may emit the same total energy if you use it longer, but it may not produce the same biological effect. PBM doesn’t reliably follow reciprocity, and irradiance, pulse structure, heat, and treatment stability all change.
Does high peak power send light deeper?
Not by itself. Depth depends on wavelength, tissue optics, beam geometry, pulse structure, contact, and surface exposure. A peak value without average power and full pulse data cannot answer the question.
Does a Class IV laser work better than a lower-power device?
Laser class is an eye-safety classification, not an effectiveness score. The complete device and protocol determine the exposure.
Does a lower laser class mean lower power?
No. Class depends on how much light can reach the eye, which depends on wavelength, beam divergence, source size, emitter spacing, pulsing, and enclosure. A probe with ten 450 mW lasers spaced apart (4.5 W total) can be Class 3B while a single laser just over 500 mW is Class 4, and some Class 1 devices are more powerful than many Class 4 lasers.
Is eye safety based on a device’s power?
Not on total power alone. Eye safety depends on how much light the device can direct into the eye, not on the combined output of all its emitters. Always follow the eye-safety instructions for the specific device, and never shine therapy lights into a person’s or pet’s eyes.
How do I know whether a company’s power number is real?
Look for a measured optical value, the instrument and calibration information, the measurement plane, the operating mode, session-length stability, and a manufacturing tolerance. Independent measurement can add confidence.
Why does fur matter if the device has enough power?
Fur can block or redirect light before it reaches the skin. Raising device output does not make delivery predictable. A device should reliably reach the skin during normal use.
Can average power tell me how much light reaches a joint?
No. It tells you the average optical output rate at the stated measurement plane. Estimating power at a deep target requires tissue-transmission data for the wavelength, anatomy, coat, geometry, and application method.
The bottom line
Most people check a device’s power to see if it’s strong enough to reach the target or to figure out how long to treat. Wavelength matters more for reaching the target, and irradiance matters more for the dose.
Average power still matters because irradiance and dose are built on it. The key word is average. A credible device should disclose measured average optical output during normal use, not just peak power or electrical wattage. That number should tie directly to treatment area, irradiance, time, total energy, pulse settings, wavelength output, and how the light reaches the skin. If it’s missing, or if it’s really a peak value, you can’t calculate an accurate dose.
Power can shorten treatment. It can also raise irradiance, heat, and the cost of a timing error. Equal joules delivered at different rates don’t necessarily produce equal biological responses, because PBM doesn’t reliably follow reciprocity.
The most useful power isn’t the biggest number. It’s the measured, stable, and controlled output that fits a complete protocol for the tissue you’re treating.
Continue The WAIT Test™
This guide covers Average Power, the second of the four components. To run the full evaluation, including the data you need and the decision rules, use The WAIT Test™ guide. The other three components:
- Wavelengths: Is it the right kind of light for the target tissue?
- Irradiance: Is the light concentrated enough to deliver the dose in time?
- Target Tissue: Does the light reach the target tissue?
The four components work together. Passing one does not compensate for missing information in another.
The WAIT Test™ was developed by MedcoVet. The framework may be shared for educational purposes as long as its four components remain unchanged and MedcoVet is credited as its creator.
The WAIT Test™ is an educational framework for comparing device specifications. It does not determine whether PBM is appropriate for a particular pet, diagnosis, or treatment site. Make treatment decisions with a qualified veterinary professional.
For every WAIT guide and tool in one place, start at The WAIT Test™ hub.
Ready to take the next step?
Book a free consultation to speak with a licensed clinician about your pet’s condition and treatment plan.
Lola
Learn more about the MedcoVet Luma and how it is designed for at-home red light therapy for pets.
Sources
Research and references
- Ando T, Xuan W, Xu T, et al. Comparison of therapeutic effects between pulsed and continuous wave 810-nm wavelength laser irradiation for traumatic brain injury in mice. PLOS ONE. 2011;6(10). PubMed
- Ash C, Dubec M, Donne K, Bashford T. Effect of wavelength and beam width on penetration in light-tissue interaction using computational methods. Lasers in Medical Science. 2017;32(8):1909-1918. PubMed Central
- California State University, Sacramento. Laser Safety Manual. Environmental Health and Safety. PDF
- Bjordal JM, Couppé C, Chow RT, Tunér J, Ljunggren AE. A systematic review of low level laser therapy with location-specific doses for pain from chronic joint disorders. Australian Journal of Physiotherapy. 2003;49(2):107-116. PubMed
- Cronshaw M, Parker S, Grootveld M, Lynch E. Photothermal effects of high-energy photobiomodulation therapies: an in vitro investigation. Biomedicines. 2023;11(6):1634. PubMed
- de Freitas LF, Hamblin MR. Proposed mechanisms of photobiomodulation or low-level light therapy. IEEE Journal of Selected Topics in Quantum Electronics. 2016;22(3):7000417. Full text
- de la Barra Ortiz HA, Parizotto NA, Liebano RE. Comparison of the effectiveness of high-intensity laser therapy versus low-level laser therapy in musculoskeletal disorders: a systematic review and network meta-analysis. Lasers in Medical Science. 2026;41(1):30. PubMed
- Enwemeka CS. Intricacies of dose in laser phototherapy for tissue repair and pain relief. Photomedicine and Laser Surgery. 2009;27(3):387-393. PubMed
- Food and Drug Administration. Laser products and instruments. FDA
- Girasol CE, Braz GdA, Bachmann L, Celli J, Guirro RRdJ. Laser light sources for photobiomodulation: the role of power and beam characterization in treatment accuracy and reliability. PLOS ONE. 2022;17(3). Full text
- Hadis MA, Zainal SA, Holder MJ, et al. The dark art of light measurement: accurate radiometry for low-level light therapy. Lasers in Medical Science. 2016;31(4):789-809. PubMed
- Hashmi JT, Huang YY, Sharma SK, et al. Effect of pulsing in low-level light therapy. Lasers in Surgery and Medicine. 2010;42(6):450-466. PubMed
- Hode L. Penetration of light into living tissue. Swedish Laser-Medical Society. laser.nu
- Hochman-Elam LN, Heidel RE, Shmalberg JW. Effects of laser power, wavelength, coat length, and coat color on tissue penetration using photobiomodulation in healthy dogs. Canadian Journal of Veterinary Research. 2020;84(2):131-137. PubMed
- Huang YY, Sharma SK, Carroll J, Hamblin MR. Biphasic dose response in low level light therapy: an update. Dose-Response. 2011;9(4):602-618. Full text
- Jacques SL. Optical properties of biological tissues: a review. Physics in Medicine and Biology. 2013;58(11). PubMed
- Jenkins PA, Carroll JD. How to report low-level laser therapy (LLLT)/photomedicine dose and beam parameters in clinical and laboratory studies. Photomedicine and Laser Surgery. 2011;29(12):785-787. PubMed
- Joensen J, Ovsthus K, Reed RK, et al. Skin penetration time-profiles for continuous 810 nm and superpulsed 904 nm lasers in a rat model. Photomedicine and Laser Surgery. 2012;30(12):688-694. PubMed
- IEC 60825-1:2014. Safety of laser products – Part 1: Equipment classification and requirements. International Electrotechnical Commission. IEC
- Lanzafame RJ, Stadler I, Kurtz AF, et al. Reciprocity of exposure time and irradiance on energy density during photoradiation on wound healing in a murine pressure ulcer model. Lasers in Surgery and Medicine. 2007;39(6):534-542. PubMed
- Leal-Junior ECP, Hess F, Dias LB, Lino MMA, et al. Light transmission and thermal impact of different photobiomodulation therapy devices on the Achilles tendon of human volunteers: a comparative study. Photodiagnosis and Photodynamic Therapy. 2025;56:105234. PubMed
- Looney AL, Huntingford JL, Blaeser LL, Mann S. A randomized blind placebo-controlled trial investigating the effects of photobiomodulation therapy on canine elbow osteoarthritis. Canadian Veterinary Journal. 2018;59(9):959-966. PubMed
- Luna SPL, Schoen A, Trindade PHE, da Rocha PB. Penetration profiles of a Class IV therapeutic laser and a photobiomodulation therapy device in equine skin. Journal of Equine Veterinary Science. 2020;85:102846. PubMed
- Millis DL, Bergh A. A systematic literature review of complementary and alternative veterinary medicine: laser therapy. Animals. 2023;13(4):667. PubMed
- Shanks S. Low level laser therapy: the power and penetration myth. Erchonia Corporation; 2008. Quotes Tunér J, Hode L. Confounders and magicians (originally published at laser.nu; no longer online).
- Sharma SK, Kharkwal GB, Sajo M, et al. Dose response effects of 810 nm laser light on mouse primary cortical neurons. Lasers in Surgery and Medicine. 2011;43(8):851-859. PubMed
- Tunér J, Hode L, Jenkins PA. How not to promote laser therapy. Swedish Laser Medical Society and Australian Medical Laser Association. laser.nu
- Shurrab K. Proposed guidelines for reporting parameters and procedures of high- and low-level laser therapy in medical research articles. Medical Devices: Evidence and Research. 2025;18:495-505. PubMed
- GembaRed. What is the real intensity of my LED panel? The dark deception of red light therapy. Full text
- IEC 62471:2006. Photobiological safety of lamps and lamp systems. International Electrotechnical Commission.


